

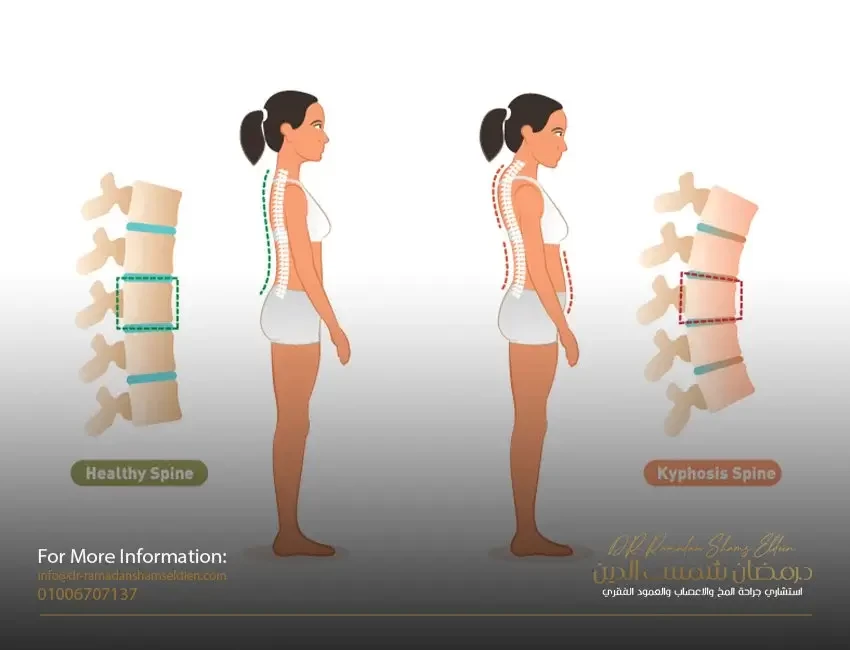
حداب العمود الفقري - وطرق التعافي منه
Introduction for kyphosis
Kyphosis, a condition characterized by an excessive outward curvature of the spine, has become a topic of increasing concern in our sedentary lifestyle era. This comprehensive guide aims to demystify kyphosis, addressing its various forms, causes, treatment options, and preventive measures. We will explore everything from the basics of what kyphosis is, to detailed discussions on surgical and non-surgical treatments, ensuring a thorough understanding of this spine condition.
What is Kyphosis?
Defining Kyphosis
Kyphosis is a spinal disorder where an abnormal curvature forms, causing a hunchback or slouching posture. It can occur at any age but is most common in older adults, particularly women. While a certain degree of curvature is normal, kyphosis refers to an exaggerated curve that can lead to various health concerns.
Types of Kyphosis
There are several types of kyphosis, but two notable ones are:
- Lumbar Kyphosis: This type involves the lower back, leading to a forward curvature that's less common but equally concerning.
- Kyphotic Spine: A general term that refers to any section of the spine affected by this excessive curvature, most commonly seen in the thoracic (upper) spine.
H3: Common Confusions
It's not uncommon to come across the term "kyposis." It's important to clarify that "kyposis" is a common misspelling of kyphosis and refers to the same condition.
Causes and Genetics of Kyphosis
Exploring the Causes
Kyphosis can stem from various factors, including degenerative diseases (like arthritis), disc degeneration, osteoporosis, trauma, or even poor posture over time. In some cases, it's present from birth due to a malformation of the spine or develops during adolescence due to unknown reasons (Scheuermann's disease).
Genetic Factors
Is kyphosis genetic? While lifestyle and environmental factors play significant roles, genetics can contribute, especially in cases like congenital kyphosis. However, having a family member with kyphosis doesn't guarantee you'll have it, but it may increase your risk.
Kyphosis in Adults
Adult vs Juvenile Kyphosis
While kyphosis can affect individuals at any age, its presentation and implications differ between adults and juveniles. In adults, kyphosis often results from conditions like osteoporosis, degenerative spine disease, or muscle weakness. It can lead to pain and mobility issues, significantly impacting quality of life. In contrast, juvenile kyphosis, particularly Scheuermann's disease, often arises during the growth spurt before puberty and may correct itself over time or require intervention if severe.
Identifying Kyphosis
Signs and Symptoms
Recognizing kyphosis involves looking for signs such as a visible hump on the back, pain in the spine, stiffness, and in severe cases, difficulty breathing due to the compression of internal organs. Pain may become more pronounced during long periods of standing or sitting.
H3: Visual Guide
To aid in identification, visual references such as kyphosis pictures can be helpful. These images typically show the noticeable curvature from the side, providing a clear contrast to a normal spine's appearance.
Kyphosis Treatment Methods
Overview of Treatments
Treatment for kyphosis varies depending on the severity and underlying cause. Options range from conservative methods like physical therapy and medication to more invasive procedures like surgery. The primary goals of treatment are to reduce pain, improve function, and prevent the curvature from worsening.
Corrective Measures
Non-surgical methods to fix kyphosis include:
- Physical Therapy: Exercises to strengthen back muscles and improve posture.
- Bracing: In some cases, especially in adolescents, wearing a brace can help correct spinal curvature.
- Medications: Pain relievers and anti-inflammatory drugs can help manage symptoms.
Kyphosis Surgery
Surgical Options
Surgery is usually reserved for severe cases of kyphosis where the curvature is significantly impacting the patient's quality of life or health. Procedures may involve spinal fusion, where vertebrae are joined together to stabilize the spine, and osteotomy, where a portion of the bone is removed to correct the alignment.
Before and After Surgery
The comparison of kyphosis surgery before and after can be dramatic, showing significant improvement in the spine's alignment. However, it's crucial to have realistic expectations and understand that surgery involves risks and a considerable recovery period.
Non-Surgical Approaches
Physiotherapy and Exercises
Specific exercises can help manage kyphosis by strengthening the back muscles and improving posture. A physiotherapist can design a personalized exercise program suited to the individual's condition.
Lifestyle Adjustments
In addition to exercises, making lifestyle changes can be beneficial. These include maintaining a healthy weight, ensuring adequate nutrition (particularly calcium and vitamin D for bone health), and practicing good posture.
Living with Kyphosis
Managing Pain
Living with kyphosis can often mean managing varying degrees of back pain. Pain management strategies include regular physical therapy, over-the-counter pain relievers, and, in some cases, prescription medications. Heat therapy and relaxation techniques can also be beneficial for reducing discomfort and improving muscle function.
Quality of Life
Kyphosis can impact quality of life, not just physically but also emotionally and socially. It's important for individuals to seek support, whether through therapy, support groups, or community resources. Adjusting daily activities to accommodate physical limitations and focusing on activities that bring joy and fulfillment can also help in maintaining a positive outlook.
Preventing Kyphosis
Prevention Strategies
While not all forms of kyphosis can be prevented, certain measures can reduce the risk or lessen the severity. These include maintaining good posture, engaging in regular exercise, especially activities that strengthen the back and core muscles, and ensuring proper nutrition for bone health.
The Importance of Early Detection
Early detection of kyphosis is crucial for effective management. Regular check-ups, especially during the adolescent growth spurt, can help in identifying any abnormal spine curvatures early on. Early intervention can often prevent the progression of kyphosis and reduce the need for more invasive treatments in the future.
Conclusion
Kyphosis, with its various forms and implications, requires a comprehensive understanding for effective management and treatment. From identifying the early signs to exploring treatment options and coping strategies, this guide aims to provide a thorough overview of kyphosis. However, it's important to remember that each case is unique, and what works for one person may not work for another. Consulting with healthcare professionals, staying informed, and being proactive about spine health are key to managing kyphosis effectively.
الإنزلاق الغضروفي القطني والآم اسفل الظهر
Lumbar herniated disc and lower back pain
Low back pain is one of the most common disorders affecting the musculoskeletal system and is considered the most prevalent in the modern era. It still poses a real health challenge in terms of prevention and treatment, and it ranks third in terms of the high cost of treatment after cardiovascular diseases and cancerous diseases.
The spine is the only longitudinal axis of the body that bears the entire weight of the trunk, and its lumbar vertebrae are connected with the pelvis and its movement with the sacral vertebrae, and accordingly, any imbalance that affects the body axis (functionally or anatomically) will negatively affect the functional level of the trunk and the movement of the body in general and thus It may reduce psychological, economic and social efficiency, especially when pain appears, which greatly affects the daily activities of the individual and the quality of life he lives. In dispersing the forces acting on it by distributing pressure on the nucleus of the cartilaginous disc, which distributes it equally on the surrounding cartilage rings in all directions over the entire area of the cartilaginous disc. The vertebral congruence condition becomes lost.
Low back pain is usually divided in terms of recurrence into acute, which occurs suddenly and often occurs once or twice in life, and chronic, which occurs frequently, cumulatively and with a higher level of severity with each time.
It is divided in terms of the type of cause into specific mechanical pain, which is directly related to the pain that results from acute muscle strain and herniated disc, which is responsible for 90% of these cases, and to non-mechanical, non-specific pain, which is indirectly related to the pain that results from anxiety states, enlargement of the prostate gland, and dryness. Herniated disc. In terms of the degree of pain, it is divided into simple, medium and severe pain.
A herniated disc (herniated disc or lumbar disc herniation) is defined as the nucleus and its rings being pushed irregularly from between the vertebrae to the back under the influence of severe pressure with the occurrence of a hernia in the cover of the cartilaginous rings, to grow towards the back to enter the spinal canal and put pressure on the spinal cord. This is called this The condition of the central compressive cartilage. Either it grows backward and to one side and presses on one of the nerve roots branching from the spinal cord. This condition is called the noncentral or lateral compressive cartilage. Regardless of the type of herniated disc or herniated disc in the lumbar disc, it causes severe defensive muscle contractions.
The range of motion between the vertebrae is reduced, in addition to the occurrence of severe pain, and the level of danger is high, as in road accidents, for example, where the pressure is very strong to cause a cartilage rupture with sharp ends that threaten to tear and injure the surrounding tissues and nerves during movement, causing partial or total paralysis of the nerve depending on the force of pressure The severity of the injury to the nerve root.
The most frequent cases are in the lumbar region between the fourth and fifth lumbar vertebrae and between the fifth lumbar and first sacral vertebrae.
Often, these patients complain of a group of severe neurological disorders represented by sensory impairment and disturbance in
The level of the reflex reaction, weakness in the muscular ability of the lower extremities or one of them, and severe pain in the direction responsible for the nerve root compressed in the herniated disc, which makes this disease a major cause to change the nature of the patient’s psychological, social, economic and family life, especially when it causes any degree of partial or partial disability. total
As for recurrent chronic cases, it is accompanied by a group of functional and anatomical changes on the lower back before the injury of a herniated disc, such as the occurrence of simple long-term muscle tension for many reasons. The cartilage disc reduces the concentration of water in that part of the cartilage, as water - despite its low concentration in the cartilage - plays an essential role in the process of distributing and spreading nutrients within the tissue of the lumbar disc and the speed of completion of vital reactions. With the persistence of muscle tension and the passage of time, this condition is called degenerative lumbar disc dehydration
Then begins a process of functional changes at the level, slowing down the speed of biochemical reactions, as well as anatomical changes in the formation of the lumbar disc, such as a lack of cartilage tissue cohesion and weakness in its elasticity and a decrease in the size and mass of the lumbar disc, so it becomes less able to absorb the forces acting on it, and the process of fibrosis of the spinal canal begins. The nerve roots exits increasingly over time to cause what is known as neural tube stenosis.
This results in sharp pains in the lower back extending to the lower extremities or one of them, with lethargy and weakness and a decrease in the ability to walk because of this, and the ability to straighten the trunk is weakened due to the contact of the cartilaginous protrusion with the nerve roots emerging from the spinal cord.
Most cases of herniated discs of the lumbar disc usually occur between the ages of twenty and forty, with most injuries occurring.
Due to improper lifting of heavy weights or injuries resulting from practicing some sports such as weightlifting and gymnastics, or for former athletes in some sports.
Herniated disc pain is treated medically
With it on the basis of removing the pressure from the cartilage of the cartilage
On the nerves by using the abduction tension
(slitting the vertebrae apart) naturally using positions
body (positional therapy) called stretching

ما هو مرض الجنف؟ وأنواعه وأشهر الأعراض
scoliosis
Scoliosis is a three-dimensional deformity of the spine and rib cage. It may develop as a single primary curve (looks like the letter C) or as two curves (a primary curve with a compensating secondary curve forming an S shape). Scoliosis may occur only in the upper back (thoracic) or lower back (lumbar), but it most commonly develops in the area between the thoracic and lumbar (the thoracic and lumbar areas). The doctor attempts to identify scoliosis by the shape, location, direction and size of the curve and, if possible, the cause. The severity of scoliosis is determined by the extent of the curvature of the spine and the angle of rotation of the trunk.
Determining and classifying the type of scoliosis often by the shape of the curve, by its location, or by its direction:
Scoliosis is classified according to the shape of the curve into structural (in other words true organic) or non-structural (which is functional or secondary). • In structural scoliosis, not only do the spine bend from side to side, but the vertebrae also rotate, resulting in a twisting of the spine . During torsion, one side of the rib cage is pushed out so that the spaces between the ribs widen and the shoulder blade protrudes (which causes the rib cage to deform or protrude); The other half of the rib cage is twisted inward, putting pressure on the ribs. • The non-structural or functional curve does not twist, but is a simple curve from side to side, and it is usually a compensation for the main structural curve or due to muscle spasms or other diseases of the vertebrae.
Determine scoliosis by its location. The location of the skeletal curve is determined by the location of the apical vertebra, which is the protruding vertebra at the apex (the highest point) of the spinal tuberosity. This particular paragraph will also undergo severe rotation.
Definition of scoliosis according to its direction. The direction of the curve in structural scoliosis is determined by whether the convex (rounded) side of the curve curves to the right or left. For example, a doctor defines a specific condition as right thoracic scoliosis if the apical vertebra is in the thoracic region (upper back) of the spine and the curvature is to the right.
The size of the curve is determined by taking length and angle measurements of the curve in an X-ray view.
Causes of scoliosis
First: idiopathic scoliosis
In 80% of patients, the cause of scoliosis is unknown. These conditions are called idiopathic scoliosis. Most cases of idiopathic scoliosis have a genetic basis, but researchers have not yet identified the gene or genes responsible for it. Researchers are investigating potential physical abnormalities that may cause bone or muscle imbalances that can lead to scoliosis. Among them are the following: muscles around the vertebrae. Some research suggests that imbalances in the muscles around the vertebrae may make children susceptible to spinal deformities as they grow. High arches in the feet. One study showed a higher incidence of abnormally high arches in the feet of people with idiopathic scoliosis, suggesting that altered balance may be a factor in some cases. Coordination problems. Some experts are looking at inherited impairments in cognition or coordination that may cause asymmetric spine development in some children with scoliosis. The investigators are also looking at possible abnormalities in collagen, an important structural protein found in muscle and bone. Other researchers are looking at a possible defective gene responsible for the production of fibrillin, an important component of the connective tissue that makes up bone and muscle. Some research has revealed abnormalities in a calcium-binding protein, calcodulin, among patients with scoliosis compared to the general population. Other researchers are still studying melatonin, a hormone secreted in the brain involved in sleep and growth. Animal studies and some human studies have found abnormalities associated with scoliosis.
Second: congenital scoliosis
Congenital scoliosis is caused by congenital abnormalities of the spine that usually involve abnormalities in the development of the vertebrae (missing or fused vertebrae). The condition usually appears around the age of two or between the ages of 8 and 13 as the spine begins to grow more rapidly, putting more stress on congenital malformations. Curves in such cases should be closely monitored, as they can progress rapidly. (Kidney problems, especially with only one kidney, often coincide with congenital scoliosis.)
Third: Scoliosis caused by genetic and medical disorders
Scoliosis may also be the result of muscle paralysis or deterioration from conditions such as myasthenia gravis, polio, or cerebral palsy. Other diseases that can cause scoliosis are Marfan syndrome, Friedreich's ataxia, Albers-Schönberg disease, rheumatoid arthritis, and osteogenesis imperfecta. Spinal cord injury may also cause scoliosis. A very rare genetic disease called familial dysautonomia has been identified as a cause of scoliosis in Jewish children of Ashkenazi descent. (It should be noted that only 500 cases have been reported globally, and this is related to the nature of the family composition of the Jews). Birth defects known to cause scoliosis include spina bifida or myelomeningocele (congenital hernia of the central nervous system).
Fourth: tumors of the vertebral column
Tumors and small growths or abnormalities in the spine may play a larger role than previously thought in the causes of scoliosis in young children. Back surgery to remove benign tumors increases the risk of spinal deformity.
Fifth: Causes of scoliosis other than structural or functional
Nonstructural scoliosis is sometimes caused by poor posture, leg length differences, and muscle spasms.
Scoliosis risk factors
General risk factors for idiopathic scoliosis. Idiopathic scoliosis (where the cause is unknown) is the most common form. It almost always occurs during a growth spurt just before and during adolescence. However, it can also occur in young children and even in infants. About 2% to 3% suffer from
Adolescents have a curvature of 10 degrees or more, but only about 0.3% to 0.5% have curves greater than 20 degrees. Mild curvature occurs equally in girls and boys, but curvature is 10 times more likely to occur in girls.
Medical risk factors. People with certain medical conditions that affect joints and muscles are more likely to develop scoliosis. About 10% of girls with Turner syndrome, a genetic disease common in women, develop scoliosis.
Young athletes. A 2000 study reported that young girls who did rhythmic gymnastics had a 10-fold greater risk of developing scoliosis. This elevated risk is likely due to three concurrent factors: an imbalance of weight on the spine, loose joints and a delayed onset of puberty. (Delayed menstruation is a common risk factor for all female competitive female athletes such as stress fractures and possibly scoliosis.)
Risk factors for the progression of curved scoliosis in affected children and adolescents
Once a mild curve is observed, the next step becomes more difficult, as it predicts whether or not the curve will progress to a more severe condition. Although as many as three in 100 teens have a condition that's serious enough to at least need observation, the likelihood of severity may be lower or above average depending on other factors.
• Being female or at a younger age at the onset of scoliosis increases your risk.
• The greater the bending angle, the greater the risk. At 20 degrees, only about 20% of the curves advance. However, young adults diagnosed with a 30 degree curve have a 60% risk of progression; With a 50 degree curve, the hazard is 90%.
• Girls who have low scoliosis and an unbalanced spine by more than an inch may be less likely to develop curves. Taller girls also appear to be at greater risk. Curvatures caused by congenital scoliosis (spine problems present at birth) may progress rapidly.
Risk factors for progression to scoliosis in adults
In rare cases, scoliosis may develop in adults who may have had unknown or untreated scoliosis in their youth. Osteoporosis or weak bones, a serious problem in many older adults, can cause mild curvatures to develop. (Osteoporosis itself is not a risk factor for the onset of new scoliosis.) However, in most cases, it is not known why adult curves progress.
How dangerous is scoliosis? Impact on the lungs and heart
The severity of scoliosis depends on the degree of curvature and whether it threatens vital organs, specifically the lungs and heart. Mild scoliosis effect (less than 20 degrees). Mild scoliosis is not serious and requires no treatment other than monitoring.
The effect of moderate scoliosis (between 25 and 70 degrees). It is still not clear if mild scoliosis causes major health problems. In one study, adults with mild scoliosis had normal lung function, although they had difficulty exercising.
The effect of severe scoliosis (more than 70 degrees). If the curvature exceeds 70 degrees, the severe twisting of the spine that occurs in skeletal scoliosis can cause the ribs to press on the lungs, restrict breathing and reduce oxygen levels. One study concluded that nearly two-thirds of patients with 90-degree curves and below had less than 80% of normal lung capacity. Abnormalities can also affect the heart and cause dangerous changes.
The effect of severe scoliosis (more than 100 degrees). Ultimately, if the curvature reaches more than 100 degrees, both the lungs and the heart can be injured. Patients with this level of risk are at risk of developing lung infections and pneumonia. Curves greater than 100 degrees increase the mortality rate, but this problem is very uncommon in America.
How is scoliosis diagnosed?
The severity of scoliosis and the need for treatment are determined by the extent of the curvature of the spine and the angle of rotation of the trunk (ATR). Both are measured in degrees. The two factors are usually related, so, for example, a person with a 20° spinal curve has a 5° ATR. This measurement used to be a standard for recommending treatment, although it is now known that up to 80% of 20° curves do not get worse. Scoliosis is diagnosed when the curve measures 11 degrees or more, but treatment is not usually required until the curve is 30 degrees and the ATR is 7 degrees.
physical examination
Forward bending test. A screening test often used in schools and in pediatric or primary care doctors' offices is called the forward bend test, in which the child bends forward with his arms hanging down, with feet together and knees straight. The curve of structural scoliosis is more pronounced when bending, and the examiner may notice an unbalanced rib cage, where one side is higher than the other, or other abnormalities. The forward bend test is not sensitive to deformities in the lower back, a very common site of scoliosis. Therefore, it misses about 15% of scoliosis cases, and many experts do not recommend this test as the only method for detecting scoliosis.
Other physical tests. The patient is usually asked to walk on the toes, then the heel, and then he is asked to jump up and down on one foot. These activities indicate leg strength and balance. The doctor will also check for tight tendons in the back of the leg, which is typical in adolescence, but may also indicate nerve root irritation or spondylolisthesis, a condition in which one vertebra slips forward over the other. The doctor will also check for nervous system dysfunction by testing reflexes, nerve sensation, and muscle function.
Recognize the curvature
Diagnosis
True is important, because poor judgment can lead to unnecessary X-rays and cumbersome treatments in children who are not at risk of progression. Unfortunately, although measurements of curves and rotation are useful, there is no test yet to determine whether or not a curve will advance. tilt (scoliometer). The clinometer (scoulometer) measures deformities of the trunk. The procedure is as follows:
The patient is asked to bend with outstretched arms and press the palms together, until a curve can be observed in the chest (upper back) area. The Scoliometer is placed on the back and is used to measure the apex (highest point) of the curve. Scoliometer results can indicate problems, and some experts believe it will be a useful tool for widespread screening. However, Scholetter's scales measure rib cage abnormalities in more than half of children who have been shown to have very little or no lateral curves. Scholetter's scales are not accurate enough to guide treatment, and if results show an abnormality, an X-ray should be performed.
Imaging tests
X-rays are currently the most cost-effective way to diagnose scoliosis. Experts hope that an accurate, non-invasive diagnostic technique can be developed that may eventually replace some of the X-rays currently used to monitor the progression of scoliosis. So far, some of these techniques appear to be fairly accurate for detecting scoliosis in the upper back (the thoracic region) but not scoliosis in the lower back (the woody region).
X ray. If the examination indicates scoliosis, the child may be sent to a specialist who takes an initial X-ray and monitors the child every few months with frequent X-rays. X-rays are necessary for the accurate diagnosis of scoliosis in several ways:
• X-rays reveal the degree and severity of scoliosis.
• An X-ray identifies any other abnormalities of the spine, including kyphosis (hunchback) and hyperlordosis (fluctuation).
• X-rays help the doctor determine whether the skeletal growth has reached maturity or not.
• X-rays of patients with curvature can help distinguish between structural and non-structural scoliosis.
Structural curves persist when a person bends, and non-structural curves tend to disappear. (It should be noted that sometimes muscle spasms or a growing spine can cause non-structural scoliosis, which shows a curve when bending.)
In children and adolescents with mild curvatures or in older adolescents with more severe curvatures, but whose growth has stopped or slowed, X-rays should be done every few months in order to detect the increased severity. Young adults with scoliosis should be sure to keep X-rays indefinitely in case back problems develop later in adulthood and need to be re-examined.
curve calculation
cup method. The degree of the curve is almost always calculated using a technique known as the Cobb method.
On an X-ray of the spine, the examiner draws two lines: one line that extends outward and upward from the upper vertebra edge of the curve. The second line extends outward and downward from the lower vertebrae. Then a vertical line is drawn between the two lines. The angle of intersection is measured to determine the degree of bending.
The Cobb method is limited because it cannot fully define the three dimensions of the spine. So they are not effective in determining spinal rotation or kyphosis. It also tends to overestimate the curve. Other diagnostic tools are needed to make a more accurate diagnosis.
A new technique that uses calculations based on geometric principles for the apex of the curve as well as the top and bottom of the curve to determine all dimensions of the curve may prove to be accurate.
Determine the end of growth
Even if the curve is calculated accurately, it is still difficult to predict whether or not scoliosis will progress. One way to predict whether or not the curvature will progress is to know when the child will stop growing. If a child has years to grow, the spine has more time to progress. If a child stops growing within a year, the progress should be very slight. (It should be noted, however, that some progression occurs in approximately 70% of the curves even after the spine has matured.)
Knowing a child's age is of course the first step in estimating the end of development. In addition, other methods have been developed to help predict the end of the growth phase.
One method is called the Risser's sign, which quantifies the amount of bone in the area at the top of the hip bone. A low score indicates that the skeleton still has significant growth; A high score means that the child has almost stopped growing and a small curve is unlikely to progress much further. The Rieser scale varies between genders and boys.
Scoliosis treatment has undergone significant changes over the past decade and a number of options are available.
treatment decision
The general rule for treating scoliosis is to monitor the condition if the curve is less than 20 degrees and consider treating curves greater than 25 degrees or those that progress by 10 degrees during monitoring. However, whether scoliosis is treated right away or just monitored is not an easy decision. The percentage of cases that will progress more than 5 degrees can be as low as 5% in certain cases and as high as 50% to 90% depending on severe curves or other predisposing factors:
• age. In general, the older the child, the less likely the curve will progress. Experts estimate that curves less than 19 degrees will progress by 10% in girls between the ages of 13 and 15 and 4% in children older than 15. (In some rare severe cases, the curvature may worsen even after treatment and the end of growth due to the pressure of body weight on the abnormal curvature.
• Gender. Girls are more likely to progress than boys.
• bending site
. Thoracic curves, those at the top of the spine, are more likely to develop from thoracolumbar curves or lumbar curves, those in the middle of the spine to the bottom.
• Intensity of bending. The higher the score, the more likely the lungs will be affected.
• The presence of other health conditions. Children in poor health may experience more stressful scoliosis treatments than other children. On the other hand, children with existing conditions that threaten lung and heart problems may need immediate and aggressive treatment.
معلومات عامة عن العمود الفقري
Backbones
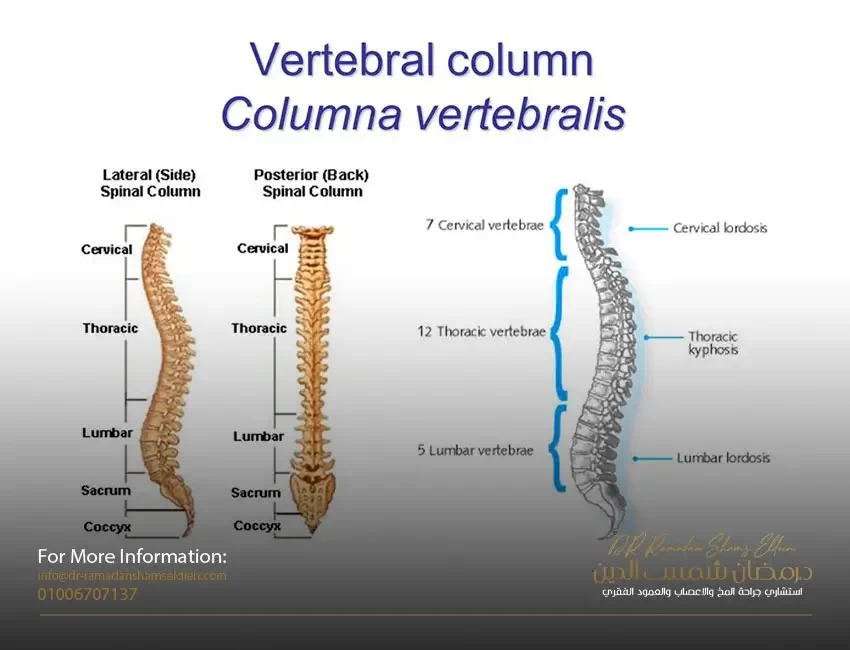
The spine is a column of small bones or vertebrae that support the entire upper body. The column is grouped into three sections of paragraphs:
• Cervical vertebrae (C) are the bones of the cervical spine and consist of seven vertebrae that support the neck and head.
• The thoracic vertebrae (T) are twelve spinal bones connected to the rib cage.
• The lumbar vertebrae (L) are the five lowest and largest bones in the spine. Most of the body weight and pressure falls on the lumbar vertebrae.
• At the bottom of the lumbar vertebrae lies the sacral vertebrae, which is a skeleton in the form of a shield that connects to the pelvis at the sacroiliac joints.
• At the end of the sacrum there are two to four small vertebrae partially fused known as the coccyx or "tail bone".
• Each paragraph can be identified using a letter and a number; The letter reflects the region (C = neck, T = chest, L = lower back, and S = sacrum), and the number indicates its location within that region. For example, C4 is the fourth lowest bone in the cervical vertebrae, and T8 is the eighth thoracic vertebra.
• The vertebrae in the spine are separated from each other by small cushions of cartilage known as intervertebral discs, known to people as vertebral cartilage. Inside each disc is a gel-like substance surrounded by a fibrous structure. The disc is 80% water, which makes it very flexible.
• Each vertebra in the spine contains a number of bony projections, known as processes. Spinal processes and transverse processes are connected to the muscles in the back and act like little levers, allowing the spine to twist or bend. The articular processes form the joints between the vertebrae themselves, they meet together and intertwine.
• Each vertebra and its processes surround and protect a central opening in the form of an arch. These arches, aligned down the spine, form the spinal canal, which surrounds the spinal cord, the central stem of the nerves that connect the brain to the rest of the body.
• The upper torso usually has a gentle external curve (kyphosis) while the lower back has a reverse internal curve (lordosis).
كل ما تود أن تعرفه عن الغدة النخامية
the pituitary gland
It is a very small gland located in the middle of the bottom of the skull, its diameter is not more than 1 cm and its weight is between 1/2 to 1 g
It is located in a small bony cavity known as the saddle above the sphenoid sinus at the bottom of the skull.
Before the twentieth century, it was prevalent among scientists that its function was to drain pituitary secretions from the brain through the nose.
With the beginning of the twentieth century, its role in hormonal control in the body was discovered, and after that, the discovery and separation of the hormones generated from it and its chemical composition and its role in controlling other tissues, organs or glands in the body.
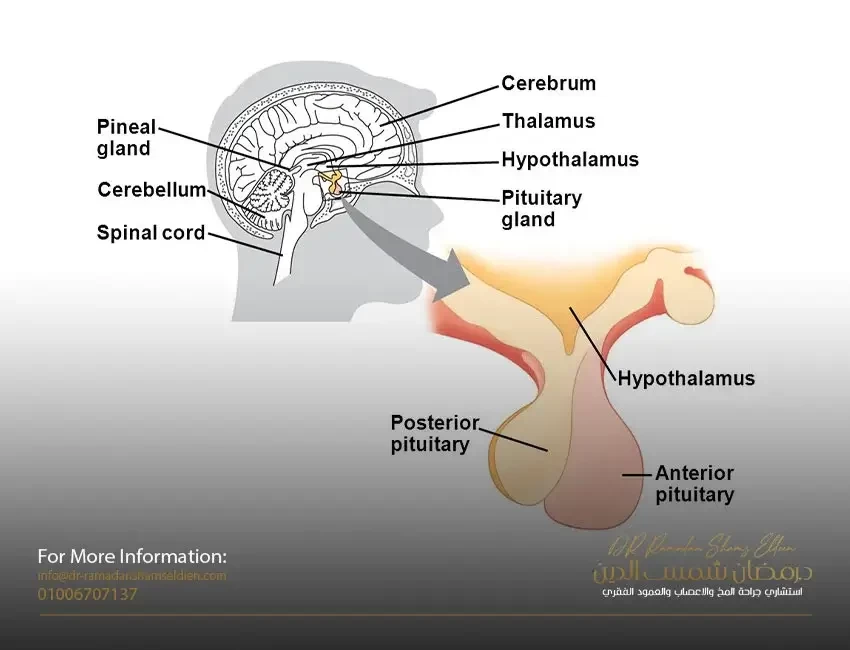
In the middle of the twentieth century, the regulatory relationship of the so-called hypothalamus with the pituitary gland was discovered, and it was a new beginning to understand the movement of hormones in the body, and that all endocrine glands are linked to the pituitary gland and the pituitary gland is directly linked to the brain through what is known as the hypothalamus.
• What is the function of the hypothalamus?
• It secretes two groups of hormones, one of which stimulates the pituitary gland and the other inhibits it
• It also contains the bodies of neurons that control the posterior lobe of the pituitary gland
Which consists???????
It consists of two parts, the anterior lobe 2/3 of the pituitary gland, which is a glandular tissue that secretes hormones
Posterior lobe 1/3 of the pituitary gland It is a nervous tissue that contains nerve endings that transmit hormones.
• When a disorder occurs in the pituitary gland, it leads to a disorder of the body as a whole in one way or another, due to the loss of the balance that we talked about earlier.
• Syndrome known as menopause or disorder and increased milk secretion.
• Of course talking about the main or central cause associated with the pituitary gland.
• Because there are many reasons for the increase in the milk hormone leading to this pathological syndrome, known as peripheral causes. (Pregnancy, breastfeeding, medications, muscle stress, psychological disorder, laziness of the thyroid gland)
The central or main reason for the increase in the milk hormone is the increase in the size of the pituitary gland due to a benign tumor in it or the hypothalamus or any pressure on the arm that connects the hypothalamus to the pituitary gland.
The most famous is pituitary adenoma
• What are the symptoms?
• In females: menstrual irregularities, constant presence of milk in the breasts, primary or secondary infertility, low sexual desire.
• In males: primary or secondary infertility, impotence, pathologically increased breast size.
• General symptoms due to direct pressure at the site of the tumor: headache, vomiting tendency, dizziness, disturbance of the field of vision, and other hormonal imbalance.
treatment
• Pregnancy: Pregnancy causes the pituitary gland tumor to shrink.
• Staying away from psychological disorders and stress, because in their presence the secretion of the milk hormone increases.
• Avoiding muscular stress in women.
• Medications: There are drugs that cause the pituitary gland tumor to shrink. Most cases of the pituitary gland leading to increased milk hormone respond to drug therapy.
Surgical intervention: In the event of symptoms resulting from direct pressure on the optic nerve, hypothalamus and vital brain tissues, direct and rapid surgical intervention is recommended.
In the case of surgical intervention, it is microscopic surgery or endoscopic surgery through the nose.
القيلة المائية الظهرية - أنواعها وكيفية علاجها
Hydrocele or myelomeningocele
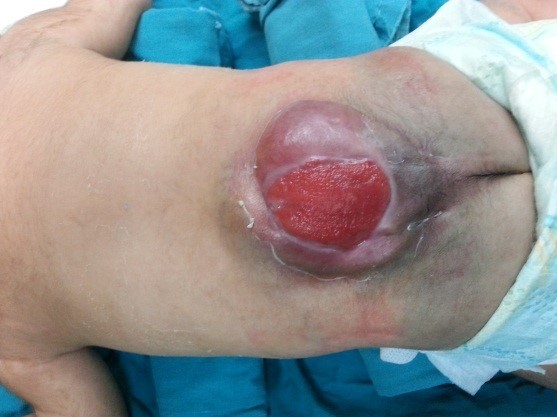
It is one of the common birth defects in our societies. It is usually diagnosed during pregnancy and is dealt with in the first days immediately after birth by doing CT scans and magnetic resonance imaging of the brain and spine. Whereas, based on the results of these tests, the diagnosis is confirmed and treatment methods and priority are determined. It is an opening in the vertebral column, which occurs when the process of closing it is not completed during the stages of embryonic development. Where the membranes surrounding the spinal cord appear outside the open vertebra, and some of the nerve-coated parts of the spinal cord emerge from the back, from the back.
Types of meningocele
1. Meningomyelocele. It is the exit of the contents of the nerve bag represented by the nerve roots with the surrounding membranes from the posterior opening of the affected vertebra. It is possible for this cyst or hydrocele to explode during childbirth with the exit of the cerebrospinal fluid, or the cyst is covered with a dark or incorrect layer of skin.
2. Meningocele. It is the emergence or emergence of a posterior cyst against the incomplete vertebra and it contains cerebrospinal fluid only. Also, this cyst or hydrocele may explode at birth with the exit of the cerebrospinal fluid, or the cyst is covered with a dark or incorrect skin layer.
3. Another case is myeloschisis. A condition in which the back skin components of the spine and the membranes are completely missing, and if we look at the back we see the spinal cord completely exposed.
Consequences of having a meningocytosis
1. Dysfunction in the nervous ability to move the lower extremities
2. Deformation of the feet or legs
3. Weakness or loss of superficial sensation in the lower extremities
4. Poor or no control over the two excreting processes
5. Intellectual performance - In general, most children with unaccompanied myelomeningocele do not have any impairment in mental functioning. But in some cases, a number of them have learning difficulties.
treatment
The obstetrician and gynecologist supervising the birth of such cases calls the neurosurgeon immediately after birth because the incision is open, it is possible for fluids to leak from the brain, and cause pollution in the central nervous system. Therefore, surgery is performed on the child during the first or second day after birth from order to close the incision. During the surgery, the incision in the back is closed, preventing fluid leakage and infection. However, the surgery does not reduce the condition of the paralysis or even the nerve damage that occurs in the part at the level of the incision and below it. It also needs to be followed up by a urologist, as many of these children need a diversion to the urethra. Children with spina bifida can lead normal and active lives. Also, most of them can walk reasonable distances with the help of a leg brace. But most likely these children will also need a wheelchair to get around. The extent of disability is related to the height and position of the affected vertebra.
أسئلة شائعة حول الانزلاق الغضروفي القطني
What is the best practical definition of a lumbar disc or herniated disc with nerve root involvement?
Local displacement of disc material or cartilage outside the normal margins or boundaries of the intervertebral disc space, resulting in pain, weakness, or numbness in the muscular or skin distribution of the compressed nerve root.
What is the natural history of a lumbar disc herniation or slipped disc with the impact of the roots?
Lumbar disc herniation will often improve regardless of the treatment method used. Unless there is neuropathy caused by direct pressure on the nerve sac and the nerve root, things will be fine over time.
What is the negative impact of a lumbar disc herniation?
The effect of lumbar disc herniation depends on the degree of slippage, as well as on the location of the displaced disc in relation to the main nerve sac and to the nerve outlet. Thus, the patient’s complaints range from mere lower back pain accompanied by pain in the lower extremities or one of them, and the complaint increases in some cases to weakness in the muscles of the foot, leg or pelvis with the inability to fully control the output.
What are the available treatment methods for lumbar disc herniation?
First: Conservative drug treatment with complete rest. The rest period extends for three weeks. The period of drug treatment extends from six to eight weeks. Taking into account the response to the treatment regimen and the lack of deterioration of the condition, which leads to a change in the treatment method followed by another method (such as surgical intervention).
Thermal frequency needle local injection
Second: physical therapy with drug therapy. Third: local injection Fourth: thermal frequency
Fifth: Surgical intervention, and surgical intervention has many types, such as the usual intervention, microscopic, endoscopy, limited intervention, vertebra stabilization, and the installation of frontal supports.
Of course, what will determine the method and quality of treatment is the patient's condition in general and the nervous condition resulting from slipping in particular.
What are the instructions to be followed for the usual medications from the patient before surgery?
• Before proceeding to the surgery, any non-steroidal anti-inflammatory drugs such as: Ibuprofen, Naprosyn, Celebrex, Mobic, Indoside and Diclofen should be discontinued. 7 days before surgery.
• You will also need to stop taking aspirin and any anticoagulants (helping with fluidity), including clopidogrel and marivan (7 to 10) days before the date of the intervention.
• Please stop taking herbal and vitamin supplements for the same period (7-10) days before surgery including but not limited to, ginseng, ginkgo biloba, vitamin E and vitamin C.
• Diabetics should not take any oral hypoglycemic drugs and switch to insulin instead of tablets 5 to 3 days before the surgical procedure.
• You should not take any diuretics on the morning of the surgery (eg Lasix) unless the patient has congestive heart failure.
• You should not take any of the classes of antihypertensive drugs, which include the following examples: Lisinopril, Lotril, Captopril, Lutensin, Monopril, Brinzide, Atacand, Benicar, Diovan and Avalid.
Duration of rest from work after surgical intervention:
Recovery after surgery varies according to your health condition before it and also according to your general fitness and physical efficiency in general before the surgical intervention, and this actually varies from person to person and is affected by many factors, such as age, smoking and chronic diseases accompanying the patient.
Therefore, the period of rest from work after the surgical intervention varies from one person to another, but it is usually not less than six or eight weeks, and not more than twelve to eighteen weeks. It is taken into account the necessity of a gradual return to work over a period of a few weeks after the completion of the rest period, so that during this period the patient avoids riding or driving a car at peak hours, standing for long periods, sitting for long periods or carrying anything heavy.
As for the owners of manual professions, they must also have a safe, gradual return to work, taking into account the previous advice. In addition, it is emphasized not to excessive manual activities and repeated payment, pulling and winding for weeks after the resumption of work.
When can I resume regular exercise?
It is recommended to rest completely in the first weeks after surgery and start exercising gradually from the fourth week on an individual basis or if necessary under the supervision of a physiotherapist.
When can I travel by plane after surgery? Although you can travel immediately after surgery, it is better after surgery for short trips to travel after at least six weeks, and for long trips, at least twelve weeks must pass. This is to avoid:
• First, the risk of developing deep venous thrombosis and the resulting risk of pulmonary arrest,
• Second, reducing lower back pain, which is the worst symptom to occur after sitting for a long time early after lumbar cartilage surgery.
In general, when allowed to travel by plane, whenever possible, it is advised to have additional legroom during travel and to change the position from sitting to walking every 20 minutes.
How to ride a car and when you can drive safely:
It is recommended to push the seat back as far as possible and maintain the straight position of the lumbar vertebrae without any curvature or curvature while you are in the car during your journey. It is preferable to lower the driving seat if possible to the lowest level while driving while maintaining the position of the vertebrae straight.
Whenever possible it is recommended, avoid sitting in the car for more than 20-30 minutes in the first 6 weeks after checking on the integrity of the wound and this is considered approximately two weeks after surgery. After two months of surgery and all is well, you can travel by car, but whenever possible,
It is recommended to break up long trips with frequent stops (every 30 minutes or 45 minutes), so that you walk for a few minutes before continuing the trip. It is also recommended to gradually drive so that we stay away from peak times and places of congestion so that we can dismantle the trip and make it easier to stop at any time.
When can I do my home activities after the surgery?
Walking
It is important to keep yourself moving and fit. You will be able to walk a distance without getting tired and it varies from person to person. Walking will not hurt the spine, as long as you keep walking in a balanced and moderate manner without twisting or bending the body. It is recommended to gradually increase the time and speed of walking after the period of complete rest after surgery (the first three weeks). It is always best to maintain a comfortable level of activity, meaning not to walk until the patient feels tired.
flexing
Bend your hips and knees, not your back.
lift
Do not lift heavy objects and always bend your knees/hips to pick up objects. When lifting, tighten your abdominal muscles before lifting. Lift what you can carry quietly without muscle fatigue, and ask others for help in carrying any weight that may strain the lumbar muscles.. Reduce the load whenever possible to several smaller loads. Whenever you are carrying anything, keep it close to your body.
صرع البالغين - الأعراض والأسباب
adult epileptic seizures
Are the epileptic seizures or convulsions that occur after adolescence for adults and the elderly.
The importance of knowing about it....it usually has a reason, that is, not just an increase in the electrical activity of the brain.
Ok, what are the reasons:
1- Superficial strokes, meaning those that occur in the cerebral cortex and move inward, will cause tension in the cerebral cortex, and thus will lead to the occurrence of an epileptic focus that leads to the occurrence of recurrent seizures.
In this case, the patient may complain of weakness or longitudinal hemiparesis on the side opposite to the place of the stroke, meaning if it is on the left side of the brain, the weakness will be on the right, and even on the right side of the brain, the weakness will be on the left side of the body,,,,, in addition to symptoms such as stuttering or lack of speech. Understanding the audible speech,,,,,,,,,,,,,, and other various symptoms according to the place or the nerve center that was affected by the stroke.
2- Brain tumors of various kinds, whether they are benign from the cerebral cortex, or malignant from brain cells, or secondary, meaning their source is any organ in the body (skin, liver, digestive system, lung, breast). The first symptom or one of the first symptoms is partial or complete convulsions (partial convulsions the patient retains his consciousness and memory during the seizure. As for the complete seizure, the patient loses consciousness and does not remember what happened to him).
3- Cerebral hematomas, in a large proportion of them are located on the cerebral cortex and as a result of their increase in size, they put pressure on the brain and put tension on the cerebral cortex and lead to the occurrence of epileptic seizures. Or without increasing the volume, it can bleed, and the hemorrhage will be the cause of the tension in the cerebral cortex, and thus the occurrence of epileptic seizures. Of course, in addition to the occurrence of accompanying symptoms, according to the location of the nevus.
4- The true arterial aneurysm is very small when it is on the cerebral cortex, because it always occurs in places where the large and medium cerebral arteries are located in minute cavities of the arachnoid pain called cerebral cisterns. But in the event of bleeding from this arterial aneurysm, it will be severe bleeding resulting from the explosion of the arterial aneurysm, and this is accompanied by a severe headache, which is the worst type of headache at all, and weakness in the cerebral nerves that come out of the brain stem (such as the nerves that move the eye, the fifth nerve, the seventh nerve,,,, ,,,,). In addition to the possibility of major epileptic seizures and impaired awareness.
5- Increasing the electroencephalogram of the brain, which leads to the occurrence of epileptic seizures, without having an organic cause from the previous causes. This will be a dysfunction as a result of an increase or deficiency of certain substances in the brain. We treat it like normal epileptic seizures, which appear in the early stages of life.6- Reasons not related to the nervous system and lead to the occurrence of epileptic seizures....and may be the result of systemic diseases or impairment of the metabolic process This is what it is, patients with liver failure Those who enter a hepatic coma will have epileptic fits and their treatment is not purely epilepsy medications. On the contrary, epilepsy medications will provide liver disease, but the treatment will be with enemas and the medications recommended by doctors in the specialization of the digestive system, endemic diseases and the liver. patients with diabetes or diabetes, in the event of a diabetic coma, the patient may also be exposed to epileptic seizures and its treatment is the treatment of diabetes not the treatment of epilepsy the coma caused by the lack or excess of sodium and potassium in the body It will have epileptic fits and be treated by specialists in critical cases and intensive care, with compensation for the decrease or increase according to the case.
Brain hemorrhage is one of the most common causes of death and also one of the very famous diseases for the occurrence of a deep coma accompanied by weakness or longitudinal hemiplegia. It is also one of the causes of sudden convulsions that occur in old age. It may occur within one or more lobes of the brain or be under the arachnoid pain or be in the ventricles of the brain or be in more than one of these places in the same The most dangerous time, of course.
The known causes are: a sharp rise in blood pressure or an eruption of a nevus, or an arterial aneurysm rupture or misuse of anticoagulants (anticoagulants).or head injuries or some late cases of patients with liver failure
The treatment is usually directed directly to control the cause, and it is usually a conservative pharmacological treatment, such as cases of high blood pressure, arteriosclerosis or liver failure problems,,,,,,,,,,,,,,,,,,,,, or an interventional cerebral catheterization such as Cases of arterial aneurysms and cerebral hematomas The one in which the bleeding is large and occupies one or more lobes in one place in the brain, and an example of this type is the rays presented to you, explaining the situation before and after the surgical removal.
كيف نحافظ علي قشرة المخ ووظايف الدماغ؟
It is not uncommon to feel disorganized and forgetful when you are under a lot of pressure. But in the long run, stress may alter your brain in ways that affect your memory.
Studies of both animals and humans clearly show that stress can affect how the brain functions, says Dr. Keri Ressler, chief scientific officer at MacLean Hospital and professor of psychiatry at Harvard Medical School. Scientists have seen changes in how the brain processes information when people experience either real-life stress or manufactured stress in a research environment. (For the latter, researchers may challenge people to perform a difficult task, such as counting down from 1073 by 13 during an evaluation.) Both types of stress appear to interfere with cognition, attention, and memory, he says.
Not only does stress affect memory and many other brain functions, such as mood and anxiety, but it also promotes inflammation, which negatively affects heart health, says Jill Goldstein, MD, professor of psychiatry and medicine at Harvard Medical School. Thus, stress has been linked to many chronic diseases of the brain and heart. Plus, it can affect men and women differently, she says.
Stress and the brain
To understand why stress affects thinking and memory, it is important to understand a little about how the brain works. Your brain is not just a single unit, says Dr. Ressler, but a collection of different parts that perform different tasks. Researchers believe that when one part of your brain is working, other parts of your brain may not have the same amount of energy to handle their vital tasks, he says. For example, if you are in a dangerous or emotionally stressful situation, the amygdala (the part of your brain that controls survival instincts) may take over, leaving the parts of your brain that help store memories and perform higher-order tasks with less energy and ability to accomplish. their own jobs. "The basic idea is that the brain diverts its resources because it is in survival mode, not in memory mode," says Dr. Ressler. This is why you may be more forgetful when you are under stress or you may experience memory lapses during traumatic events.
Goldstein says the effect of stress on the brain and body may also vary depending on when it occurs in a person's life path. Certain hormones, known as gonadotropins — which are secreted in large amounts during fetal development, puberty, and pregnancy, and are depleted during menopause — may play a role in how stress affects an individual, Goldstein says. "For example, a drop in the gonadotropin estradiol during menopause may change how our brain responds to stress," she says.
Protect yourself from harmful stress
To better handle stress, consider how you can reduce the factors that make it worse. Here are some tips that can help you manage stress better and hopefully prevent some of the harmful effects it may have on your brain.
Put some control over your posture. If stress is not expected, focus on controlling things. "A routine is good for development and health," says Dr. Keri Ressler, MD, professor of psychiatry at Harvard Medical School. Predictability fights stress.
Get a good night's sleep. Stress can lead to sleep difficulties, and the resulting lack of sleep can exacerbate stress. "Sleep deprivation makes the parts of the brain that deal with high-level functions work less well," says Dr. Ressler. Having healthy sleep habits can help. This includes going to bed and getting up at the same time each day, avoiding caffeine in the afternoon, and creating a restful sleep environment.
Be organized. Using strategies to help manage your workload can also reduce stress. For example, each day create a specific list of tasks you need to get done. This way, your homework won't seem overwhelming. Setting up the list also gives you a clear end point so you know when to finish. "Doing tasks like this helps reduce the feeling that the brain is being bombed," he says. It can also help you predict when you're likely to be stressed.
Get help if you need it. Communication can help you become more resilient and better able to manage stress, which may ultimately protect your brain health. Early intervention may reduce disability from later stress-related complications.
Change your attitude toward stress. “Life without stress is not only impossible, but also potentially uninteresting — in fact, a certain degree of stress is beneficial for growth,” says Dr. Ressler. So, instead of striving for zero stress, strive for healthy responses to stress.
Long-term brain changes
There is evidence that chronic (ongoing) stress may actually rewire your brain, says Dr. Ressler. Scientists have learned that animals that are under stress for a long time have less activity in the parts of the brain that deal with higher-order tasks - for example, the prefrontal cortex - and more activity

معلومات عن متلازمة الانحدار الذيلي
Caudatic regression syndrome is a disorder that impairs the growth of the lower (caudal) half of the body. Affected areas can include the lower back, extremities, genitourinary system, and gastrointestinal tract.
It occurs in 1 to 2.5 per 100,000 newborns. This condition is more common in infants born to mothers with diabetes when it affects 1 in 350 newborns.
Other names for this syndrome: caudal dysgenesis syndrome, caudal dysplasia sequence, caudal regression sequence, sacral agenesis
Sacral defect with anterior meningocele
In this disorder, the bones of the lower spine (vertebrae) are often deformed or missing, and the corresponding parts of the spinal cord are also irregular or missing. Affected individuals may have incomplete closure of the vertebrae around the spinal cord, a fluid-filled sac on the back covered with skin that may or may not contain part of the spinal cord, or tufts of hair at the base of the spine. People with caudal regression syndrome can also have an abnormal side-to-side curvature of the spine (scoliosis). Spinal deformities may affect the size and shape of the chest, leading to breathing problems in some individuals.
Problems with the genitourinary system in caudal regression syndrome are very diverse. Often the kidneys are deformed. Defects include a missing kidney (unilateral aneurysm), fusion of the kidneys together (horseshoe kidney), or duplication of the tubes that carry urine from each kidney to the bladder (ureteral duplication). These renal abnormalities can lead to recurrent urinary tract infections and progressive kidney failure. In addition, affected individuals may have a protrusion into the bladder through an opening in the abdominal wall (bladder exstrophy). It causes damage to the nerves that control bladder function, a condition called neurogenic bladder.
People with caudal regression syndrome may have abnormal twisting (malrotation) of the large intestine, blockage of the anus (anus), soft outer pouches in the lower abdomen (inguinal hernia), or other abnormalities of the digestive system. Affected individuals often become constipated and may experience a loss of control over their bladder and bowel functions.
Caudal regression syndrome is a complex condition that may have different causes in different people. The condition is likely caused by the interaction of multiple genetic and environmental factors. One of the risk factors for the development of caudal regression syndrome is the presence of diabetes in the mother. It is thought that increased blood sugar levels and other metabolic problems related to diabetes may have a detrimental effect on fetal development, increasing the likelihood of caudal regression syndrome. The risks to the fetus increase if the mother's diabetes is poorly managed. Paralytic regression syndrome also occurs in infants of non-diabetic mothers, so researchers are trying to identify other factors that contribute to the development of this complex disorder.
متلازمة ذيل الحصان - كل ما تود أن تعرفه
Cauda equina syndrome
It is a rare condition with a disproportionately high legal profile. It frequently occurs after a herniated (bursting) or a large prolapse of the lumbar disc (cartilage) in the middle or center area where the disc or cartilage is against the entire lumbosacral nerve bundle. A review of research indicates that about 70-50% of patients suffer from urinary retention and that 50-30% have incomplete symptoms when presented to a specialist. And this last group would benefit greatly if it was scanned by magnetic resonance imaging and a surgical procedure was performed by an experienced surgeon, as this would avoid the full complications of this dangerous syndrome.
identification
Sye syndrome is usually characterized by the so-called 'red flag' symptoms:
(LBP) • Severe lower back pain
• Sciatica: often bilateral in the lower extremities or one of them more than the other and it is possible the absence of this symptom in some cases
• Total fall or partial weakness of the feet
Urinary retention, bladder and bowel wall weakness, and sexual weakness.
It is critical, both from a medical and a legal medical perspective, that all or all of these “red flag” symptoms are identified and documented.
In particular.
background
Also, when a moderate or even simple lumbar disc herniation occurs in the presence of congenital stenosis of the lumbar neural tube, saddle horse syndrome occurs. Other than cases of lumbar disc herniation, or what is known as lumbar disc herniation, there are less common causes of this syndrome. These causes include: a dura mater tumors, infections, primary and metastatic (or secondary) tumors, trauma after surgery, after spinal anesthesia, epidural hematoma, and finally injuries that lead to direct pressure on the nerve bundle in this area, such as gunshot wounds or fractures. .
It is believed that the incidence rate in the population ranges from 1 in 33,000 to 1 in 100,000 in some European countries and is usually the result of a sudden lumbar disc herniation, except for some rare causes that we mentioned before.
The medical and legal dispute in Cauda equina syndrome occurs because of the disagreement in the understanding and outcome of some issues related to this disease. These controversial issues are:
1. The importance of delays in diagnosis and referral to hospital.
2. Risks and benefits of emergency surgery versus urgent surgery.
3. The importance of surgical delay after 24 and 48 hours.
4. The predictive significance of the involvement of the complete bladder sphincter versus the incomplete and thus the occurrence of urinary retention and complete sensory deficit versus incomplete sensory deficit.
5. Significance of signs of foot drop and unilateral and bilateral leg weakness.
6. Adverse effects of delay on the more powerful roots of the sciatic nerve.
Symptoms and diagnosis
The patient suddenly complains of a set of symptoms and shows some signs that must be quickly explained when the patient is presented to the primary medical service providers, due to the necessity of referring him to specialists. These symptoms and signs are; Severe lower back pain,,, right and left bilateral sciatica pain when the complete syndrome appears or one of them in the incomplete,,,, a complete fall of the feet in the case of the full syndrome syndrome or one of them in the case of the incomplete syndrome,,,,,, Resulting urinary retention About bladder sphincter weakness The diagnosis is made urgently by performing an MRI scan on the lumbar and sacral vertebrae to find out the cause, which, as we mentioned before, is often a sudden rupture or herniation of the lumbar disc in the central region against the fourth, fifth or fifth lumbar and first sacral vertebrae.
treatment
Urgent surgical intervention at the time the diagnosis is achieved by the specialist before 48 hours have passed from the occurrence of symptoms is the only way to cure this syndrome. This is done through a good expansion of the nerve canal and nerve roots at the site of injury with a discectomy or herniated cartilage. The sooner the intervention, the better the result and the faster the recovery. Also, the intervention in the syndrome of incomplete symptoms, the result of recovery is better than the completed one.
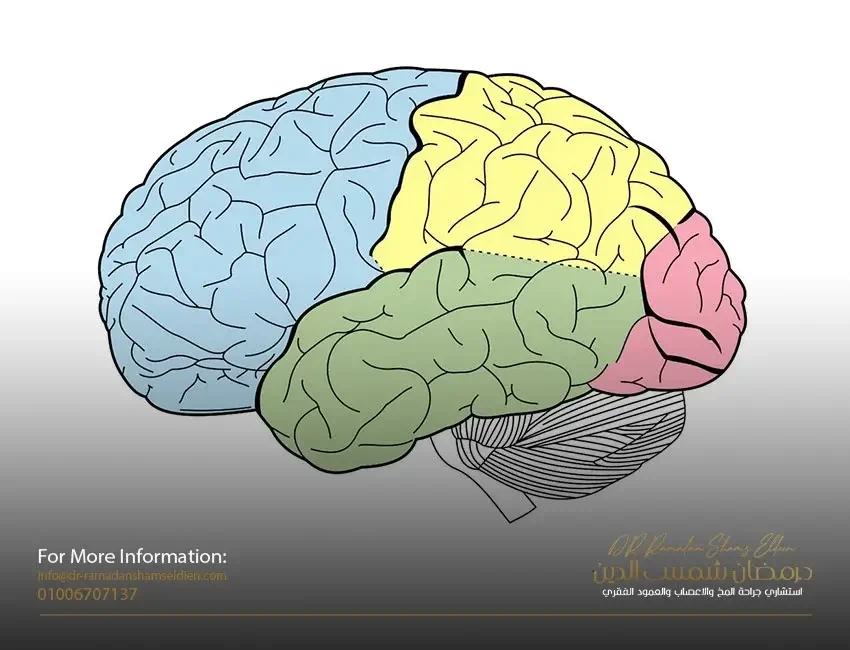
وظائف المخ بشكل مبسط
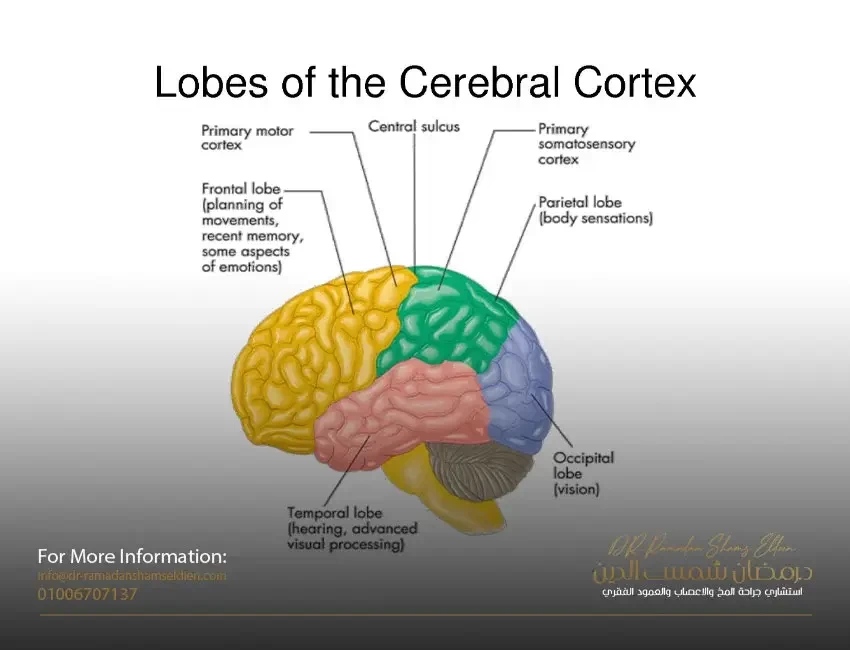
The cerebral cortex is made up of tightly packed neurons, the wrinkled layer, of coils of neurons that surround the brain from the outside. It is also responsible for higher thinking processes including speech and decision making. The cortex is divided into four different lobes, the frontal or frontal, parietal or lateral, temporal or temporal, and occipital or posterior, and each of these four lobes is responsible for processing different functions or types of sensory information.
You can use the frontal or frontal lobe almost every day.
You can use it to make decisions, such as to eat or drink, as well as to think and study.
The frontal lobe is also where our personality is formed and where we can perform higher mental processes such as planning.
In addition, the frontal lobe is necessary for a person to be able to speak fluently (without error) and with meaningful words.
The parietal lobe performs some very specific functions. As part of the cortex, it has a lot of responsibilities and must be able to process sensory information within seconds.
The parietal lobe is where information such as taste, temperature and touch is incorporated or processed. If the parietal lobe was damaged, humans would not be able to feel sensations such as touch, temperature, and taste.
The temporal or temporal lobes mainly function around hearing and selective listening.
It receives sensory information such as sounds and speech from the ears.
It is also the key to being able to comprehend, or understand purposeful speech.
In fact, we would not be able to understand a person speaking to us, if the temporal lobe did not exist.
The occipital or posterior lobe is important to be able to properly understand what the eye sees. It has to work super fast to process the fast information that our eyes send.
Similar to the temporal lobe in auditory information, the occipital lobe is in visual information so that we can understand it. If we have a weakness in the occipital lobe or an injury we will not be able to process the visual signals properly, and thus visual confusion may result.
The cerebellum is one of the most recognizable parts of the brain due to its unique shape and location.
It is extremely important to be able to perform daily voluntary tasks (doing with purpose and intent) such as walking and writing.
It is also essential to be able to stay balanced and straight.
Patients who have suffered from cerebellar damage often struggle to maintain their balance and maintain proper muscle coordination and often cannot do this normally and completely.
The hypothalamus is like a doctor who diagnoses, or identifies, a patient's illness or disease. It diagnoses the various sensory information that is transmitted to the brain including auditory (related to hearing or sound), visual, tactile, and taste cues. Next, it directs sensory information to different parts and lobes of the cortex. If this part of the brain is damaged, all the sensory information will not be processed and sensory confusion will result.
The hypothalamus is mainly responsible for motivational behavior.
This is why we know we are hungry or thirsty.
The hypothalamus also helps the body maintain a constant temperature.
This part of the brain also controls the pituitary gland, which is the main gland that controls all other endocrine glands in the body. Thus, the hypothalamus plays a major role in connecting the endocrine system with the nervous system.
The amygdala When you think of the amygdala, you should think of one word: fear. The amygdala is the reason we fear things that are out of our control. It also controls the way we react to certain stimuli, or events, that we see as threatening, the first of which is potential danger.
The hippocampus has a unique shape, similar to the shape of a horseshoe and a unique name. It is also the fortress of deep and lasting memory. The permanent storage place for all the information, experiences and events of a person throughout his life. We wouldn't even be able to remember where our home was without the hippocampus working. It has been proven that Alzheimer's disease (a disease that affects the elderly and often leads to memory loss) appeared as a result of a defect in this region of the brain.
The corpus callosum or the corpus callosum is the part of the brain that allows communication between the two hemispheres of the brain. It is responsible for transmitting nerve messages between the right and left hemispheres of the brain.
If we divide the brain into two equal halves, we will have a right and a left hemisphere. Although they are equal in size, these two aspects do not have the same functions.
The left side of the brain is responsible for controlling the right side of the body. It also performs tasks related to logic, such as in science and mathematics. On the other hand, the right hemisphere coordinates the left side of the body, and performs tasks related to creativity and the arts. Both cerebral hemispheres are connected by the corpus callosum and serve the body in different ways.
The bridge or arch serves as a message station between several areas of the brain. It helps relay messages from the cortex and cerebellum. Without it, the brain would not be able to function because messages would not be able to be transmitted. It also plays a major role in sleep and dreaming, or the state of sleep where the dream is most likely to occur, and has been shown to originate in the pons region.
The medulla oblongata is easily the most important part of the brain. Where it controls and performs all involuntary functions without thinking. In fact, we would not be able to live without the marrow because of the myriad of critical functions it performs including regulating blood pressure and breathing. As part of the brainstem, it helps transmit nerve messages from the brain to the spinal cord.
How do we keep all these various brain functions dynamically and active all the time:
First, stay away from smoking
Smoking damages the nervous system in a large number of ways, both in the short and long term.
Mental stress, thinking and pressures of daily life in excess of the usual.
Sleep deprivation or sleep disturbance causes the parts of the brain that handle high-level functions to function less well
Malnutrition.

















أعراض العصب السابع قبل حدوثه
Symptoms of the seventh cranial nerve before it occurs are a source of concern, especially when a person notices pain around the ear or a slight change in the movement of the facial muscles and then wonders whether these signs could be a precursor to facial paralysis. The seventh cranial nerve is responsible for moving most of the facial muscles and also contributes to taste, tear production, and saliva production; therefore, its dysfunction may cause noticeable and bothersome symptoms. However, there is no fixed or confirmed list of symptoms that precede inflammation of the seventh cranial nerve in every person. The condition may sometimes begin with sudden weakness over a few hours or two days without any clear warning. Ear pain or numbness may also result from other causes, such as an ear infection, dental problems, or peripheral nerve disorders. This article explains the differences between early signs and actual symptoms, as well as the causes, diagnosis, and treatment of seventh cranial nerve inflammation, while highlighting the signs of a stroke that require immediate emergency care. The following information is educational and does not replace a direct medical examination.
15 Symptoms of the Seventh Cranial Nerve Before It Occurs
Symptoms of the seventh cranial nerve before it occurs are subtle warning signs. Paying attention to them may ensure a faster recovery and help you avoid complications of facial paralysis. Therefore, visit Dr. Ramadan Shams El-Din’s clinic for proactive intervention as soon as you notice any of the following 15 signs:
-
Sudden or throbbing pain behind the ear on the side at risk of being affected.
-
A feeling of mild tingling or numbness that gradually spreads across one half of the face.
-
A noticeable change in the sense of taste, especially in the front part of the tongue.
-
Excessive and bothersome sensitivity to loud sounds in one ear (hyperacusis).
-
Unexplained dryness of the eye or mouth as a result of the involvement of the lacrimal and salivary glands.
-
A sudden increase in tearing from one eye without an obvious reason.
-
Slight difficulty fully closing the eyelid or blinking normally.
-
Mild, recurring twitching or spasms in the muscles at the corners of the mouth or eyes.
-
A feeling of heaviness in the facial muscles when trying to smile or speak.
-
Difficulty controlling saliva, causing it to dribble from the corner of the mouth.
-
Pain extending from behind the ear to the lower jaw or neck.
-
An unusual migraine-like headache that precedes the appearance of clear paralysis signs.
-
Difficulty pronouncing certain letters or words clearly because of weakened lip muscles.
-
A feeling of stiffness in the neck muscles on the side that will be affected.
-
A slight change in facial features when looking in the mirror, such as the disappearance of forehead wrinkles.
What Are the Symptoms of Seventh Cranial Nerve Inflammation?
The clear pathological signs of the condition differ from the symptoms of the seventh cranial nerve before it occurs. The nerve dysfunction gradually develops into sudden paralysis of one side of the face. This rapid progression requires urgent medical intervention under the supervision of Professor Dr. Ramadan Shams El-Din to ensure a proper diagnosis.
Once the inflammation worsens and the nerve is fully affected, a number of clinical signs that interfere with the patient’s daily functions appear. The most prominent include:
-
Noticeable drooping on the affected side of the face, with severe difficulty smiling or displaying facial expressions.
-
Complete inability to raise the eyebrow or wrinkle the forehead on the affected side of the face.
-
Severe difficulty closing the eye completely, requiring immediate protection from dryness and ulceration.
-
Food collecting on one side of the mouth and difficulty drinking without liquids leaking from the corner of the lips.
-
Clear impairment in the pronunciation of sounds and difficulty speaking clearly because of weakened mouth muscles.
Causes of Seventh Cranial Nerve Inflammation
To understand the causes behind the appearance of symptoms of the seventh cranial nerve before it occurs, Dr. Ramadan Shams El-Din’s clinics rely on accurate examinations to identify the factors that lead to nerve swelling. The most prominent include:
-
Various viral infections, such as the herpes simplex virus or shingles.
-
A sudden weakening of the immune system as a result of severe stress or chronic diseases.
-
Sudden direct exposure to cold drafts.
-
Acute middle-ear infections that extend to affect the facial nerve.
Can Symptoms of the Seventh Cranial Nerve Appear Before It Occurs?
Yes. Symptoms of the seventh cranial nerve may be detected a few days before it occurs, helping to prevent sudden paralysis. Dr. Ramadan Shams El-Din emphasizes that paying attention to these warning signs is the first line of defense for protecting the facial nerve and receiving immediate treatment at our clinics.
These early indicators may appear in different forms and require a careful examination. They include:
-
Mild pain or intermittent tingling concentrated behind the ear.
-
Slight changes in sensation or numbness in one half of the face.
-
A sudden disturbance in the sense of taste without an obvious cause.
Why Are the Early Symptoms of the Seventh Cranial Nerve Important?
The greatest importance of detecting symptoms of the seventh cranial nerve before it occurs lies in increasing the chances of complete recovery and avoiding permanent complications. Rapid medical intervention significantly reduces the extent of swelling and pressure on the facial nerve fibers.
As your strategic partner throughout your recovery journey, Dr. Ramadan Shams El-Din is committed to applying immediate treatment protocols as soon as signs are detected. This proactive approach helps ensure that you regain your health safely and quickly.
Early attention to these warning signs provides important medical benefits, most notably:
-
Maximizing the benefit of medication during the first 72 hours (the golden window).
-
Preventing permanent damage or atrophy of the muscles responsible for facial expression.
-
Shortening the recovery period and enabling a rapid return to normal life with confidence.
Treatment of Seventh Cranial Nerve Inflammation
Controlling symptoms of the seventh cranial nerve before they occur or after they worsen requires comprehensive and early medical intervention. At Professor Dr. Ramadan Shams El-Din’s clinics, we provide an integrated treatment plan tailored to your condition to help restore normal facial movement.
Medication for Seventh Cranial Nerve Inflammation
Medication is the first step in controlling inflammation and effectively reducing swelling of the facial nerve. At our clinics, we follow the latest international medical protocols to ensure a rapid response and avoid complications.
The medication plan prescribed by Dr. Ramadan Shams El-Din may include:
-
Corticosteroids to rapidly reduce inflammation and swelling of the nerve.
-
Antiviral medications if the underlying cause is a viral infection.
-
Effective painkillers to relieve the pain associated with the condition behind the ear.
Physical Therapy and Facial Exercises for the Seventh Cranial Nerve
Physical therapy is an essential part of recovery, helping to rehabilitate the facial muscles and prevent atrophy. We provide advanced rehabilitation programs that help accelerate healing and accurately restore facial expressions.
Our advanced physical-therapy techniques include:
-
Mild electrical stimulation to activate the affected muscles and nerves.
-
Customized facial exercises to improve motor control of the lips and eyes.
-
Warm compresses and gentle massage to improve circulation in the face.
Protecting the Eye from Complications of the Seventh Cranial Nerve
Eye protection is a top medical priority because eyelid weakness can lead to severe dryness and corneal ulcers. Dr. Ramadan is committed to providing strict preventive care to preserve visual health throughout treatment.
We provide precise medical guidance to protect the eye from complications, including:
-
Using moisturizing drops (artificial tears) regularly throughout the day.
-
Gently covering the eye with medical tape during sleep.
-
Wearing protective glasses to shield the eye from dust and air currents.
Diagnosis of Seventh Cranial Nerve Inflammation
The diagnosis of seventh cranial nerve inflammation, also known as Bell’s palsy, primarily depends on a careful clinical examination performed by a specialist. There is no single laboratory test that definitively confirms the condition. Instead, doctors rely on observing visible symptoms and facial-muscle movement. The patient may be asked to perform simple facial expressions, such as smiling broadly, closing the eyes tightly, raising the eyebrows, or frowning. These simple movements help the doctor assess the extent of muscle weakness and determine whether the right side, the left side, or both sides are affected, in addition to ruling out other neurological causes that may resemble this inflammation.
How Is Seventh Cranial Nerve Inflammation Detected?
In addition to the clinical examination, the doctor may use several tests and medical tools to confirm the diagnosis and rule out more serious conditions, such as strokes or tumors:
-
Electromyography (EMG): Used to measure the electrical activity of the facial nerve and its ability to conduct nerve signals. This helps determine the extent of damage and the likelihood of recovery.
-
Imaging tests (magnetic resonance imaging, MRI, or computed tomography, CT): Performed to rule out other causes that may compress the facial nerve, such as tumors or fractures in the surrounding bones.
-
Blood tests: Requested to detect any bacterial or viral infection associated with the condition, such as Lyme disease, or diabetes, which increases the risk of developing it.
Complications of Seventh Cranial Nerve Inflammation
Although most cases recover completely within a few weeks or months, some severe cases or cases that do not receive appropriate treatment may experience permanent complications:
-
Permanent damage to the facial nerve: Severe damage may prevent some facial muscles from fully regaining movement.
-
Synkinesis: Irregular regrowth of nerve fibers, causing one muscle to contract involuntarily when another muscle is moved—for example, the eye closing automatically when smiling.
-
Dryness and corneal ulcers: The inability to fully close the affected eye exposes it to persistent dryness and infections that may affect vision.
-
Partial or complete loss of taste: This may occur on the affected side of the tongue.
Is Seventh Cranial Nerve Inflammation Serious?
In general, seventh cranial nerve inflammation is not considered life-threatening and usually responds very well to treatment. Most patients recover completely within a period ranging from a few weeks to several months. However, the real danger lies in delaying early treatment, particularly during the first days after symptoms appear. Paying attention to the early signs or the symptoms of the seventh cranial nerve before it occurs—such as pain behind the ear or mild numbness—greatly helps ensure prompt intervention and the use of appropriate anti-inflammatory medications and doses, reducing the likelihood of facial deformity or permanent weakness in facial movement.
Does Seventh Nerve Paralysis Cause Harm?
Seventh nerve paralysis may result in certain harms and side effects, especially if the injury is severe or left untreated. Most of these problems occur because of impairment of the seventh cranial nerve and reduced function. The most prominent include:
-
Eye problems and twitching: The inability to close the eye completely causes corneal dryness, which may lead to ulcers and permanent visual damage if moisturizing drops are not used regularly.
-
Changes in taste and muscle spasms: The patient may notice reduced taste sensation or involuntary facial movements when attempting to smile or speak (synkinesis).
-
Psychological and social effects: Distress caused by the sudden change in facial appearance may lead to anxiety in some people. For this reason, noticing symptoms of the seventh cranial nerve before it occurs and promptly consulting a doctor are essential steps for avoiding these harms and limiting their lasting effects.
Prevention of Seventh Cranial Nerve Inflammation
Although it is difficult to prevent the condition completely because some of its exact causes remain unknown, a number of health recommendations may reduce the likelihood of developing it. It is always advisable to avoid sudden, direct exposure to cold drafts, especially after leaving warm places. Controlling blood sugar levels and reducing stress and psychological anxiety also play an important role in strengthening the nervous system. In addition, paying attention to what is known as symptoms of the seventh cranial nerve before it occurs—such as pain extending behind the ear or an immediate change in the sense of taste—helps facilitate rapid preventive and therapeutic measures before the condition worsens and fully affects the face.
Signs of Improvement in the Seventh Cranial Nerve
Recovery from Bell’s palsy usually begins gradually within a few weeks after treatment starts. The patient may notice several positive indicators showing that the nerve is regaining its normal functions:
-
Regaining facial-muscle movement: Beginning to close the eye more effectively or move the corner of the lip when smiling.
-
Reduced pain intensity: A gradual decrease in pain or discomfort around the ear and neck, which initially resembled symptoms of the seventh cranial nerve before it occurred.
-
Return of the sense of taste: Improvement in taste in the front part of the tongue and its return to normal.
-
Improved tear and saliva production: Balanced fluid production in the eye and mouth and the disappearance of severe dryness.
Seventh Cranial Nerve Inflammation in the Ear
The facial nerve follows a close course through the middle ear. For this reason, the initial symptoms often include discomfort or pain extending through this area. You may feel pressure or heaviness behind or inside the ear, sometimes accompanied by increased sensitivity to loud sounds because of the involvement of the small stapedius muscle responsible for regulating sound. In some cases, this early pain resembles symptoms of the seventh cranial nerve several days before it occurs. The ear may be the initial site of nerve swelling and compression within the narrow bony canal before facial-muscle paralysis becomes clearly apparent.
Mild Seventh Cranial Nerve Inflammation
The term mild seventh cranial nerve inflammation refers to cases in which the injury is minor and limited. The patient does not lose full movement of the facial muscles; instead, there is only slight weakness or laxity that may not be noticeable without close observation. The chances of complete recovery are very high in these cases and recovery usually occurs within a few weeks. Early diagnosis and awareness of the symptoms of the seventh cranial nerve before it occurs help keep the injury at this mild level, enabling the doctor to prescribe anti-inflammatory medications and appropriate treatment promptly to prevent worsening swelling or nerve damage.
Daily Tips for Relieving Symptoms of the Seventh Cranial Nerve
Here are the most important daily tips for managing the condition and accelerating recovery:
-
Continuous eye care: Use moisturizing drops during the day and ointments before bedtime. Make sure to wear sunglasses to protect the eye from dust and dryness caused by the inability to close it completely.
-
Adherence to medication: Take corticosteroids, antivirals, and nutritional supplements (such as B-complex vitamins) at the prescribed times according to the doctor’s instructions.
-
Continue rehabilitation exercises: Perform facial exercises slowly and with concentration in front of a mirror for several minutes each day, without excessive muscle strain, to gradually activate movement.
-
Apply warm compresses: Place warm compresses on the affected side of the face and the area behind the ear to relieve muscle tension and improve circulation.
-
Gentle facial massage: Massage the cheek, forehead, and jaw muscles with your fingertips using gentle circular movements to stimulate the muscles and nerve.
-
Avoid direct air currents: Avoid sudden exposure to air from an air conditioner or fan, especially when moving from a warm place to a cold one.
-
Reduce stress and psychological pressure: Get enough rest and sleep, as psychological relaxation supports the nervous system’s ability to recover.
-
Modify the way you eat: Grind food or eat it in small bites. Drink liquids through a straw to make swallowing easier and overcome weakness of the mouth muscles.
The Most Important Facial Exercises for Treating the Seventh Cranial Nerve
Physical therapy and facial-rehabilitation exercises play a central role in retraining the muscles and properly activating nerve signals. These exercises are preferably performed slowly and with concentration in front of a mirror several times a day:
-
Eyebrow-raising exercise: Try to raise the eyebrows slowly. You may use your fingers to help the affected side move upward.
-
Eye-closing exercise: Try to close the eyes gently and then squeeze them slightly without excessive strain. Repeat several times.
-
Smiling and pursing exercise: Smile while showing the teeth evenly, then purse the lips as if preparing to whistle to activate the mouth muscles.
-
Cheek-puffing exercise: Close the mouth and inflate the cheeks with air, then gradually move the air from one side to the other to coordinate cheek movement.
These regular exercises help restore the face’s natural flexibility and reduce the likelihood of irregular muscle contractions after recovery.
Reasons for Delayed Recovery in Patients with Seventh Cranial Nerve Inflammation
Recovery time from Bell’s palsy varies from one person to another based on several biological and medical factors that directly affect the speed at which strained nerve fibers regenerate. Delaying early medication is one of the main reasons for slow recovery. Neglecting the first days, including taking anti-inflammatory medication, leads to increased swelling and pressure on the nerve inside the narrow bony canal. Dr. Ahmed Hossam, a consultant in neurosurgery, also emphasizes that paying attention to early signs such as symptoms of the seventh cranial nerve before it occurs is the key factor in determining the recovery period. Rapid intervention during the first 72 hours helps protect the nerve from advanced damage and shortens recovery to a few weeks rather than allowing it to extend for many months.
Factors That Delay Recovery from Seventh Nerve Paralysis
Several factors and health conditions may hinder the regeneration of nerve tissue and cause facial-muscle weakness to persist longer than usual. The most prominent include:
-
Severity of the initial nerve damage: If the inflammation is acute and causes partial disruption or severe damage to the sheath surrounding the nerve, regrowth takes longer before the muscles regain normal movement.
-
Coexisting chronic diseases: Poorly controlled diabetes is one of the most important factors delaying nerve healing and proper blood flow, in addition to high blood pressure and impaired immunity.
-
Advanced age: Nerves tend to respond and regenerate more slowly in older adults than in younger age groups.
-
Neglecting physical and rehabilitation therapy: Failure to adhere to daily facial exercises or performing them incorrectly may cause muscle inactivity or synkinesis, thereby prolonging recovery.
-
Psychological stress and physical exertion: Continuous nervous tension and lack of sleep weaken the immune system and reduce the body’s ability to fight inflammation and heal the affected nerve.
-
Ignoring the initial signs of the condition: Failing to recognize the symptoms of the seventh cranial nerve before it occurs may allow complete facial paralysis to develop before antiviral medication and corticosteroids are given, increasing the complexity of the condition.
When Should You Consult a Doctor if Symptoms of the Seventh Cranial Nerve Appear?
A rapid response as soon as facial changes are noticed is a crucial step that can make a difference in recovery speed and help prevent permanent complications. You should consult a doctor immediately if you experience any numbness or sudden weakness on one side of the face, or unusual difficulty fully closing one eye. Dr. Ahmed Hossam stresses that receiving treatment within the first 48 to 72 hours after the condition begins directly helps reduce swelling around the nerve and prevent extensive damage. Paying attention to what is known as symptoms of the seventh cranial nerve before it occurs—such as sudden, sharp pain behind the ear or an unexplained change in taste—requires immediate medical evaluation before muscle weakness worsens and becomes fully apparent in the facial features.
Difference Between Symptoms of the Seventh Cranial Nerve and Stroke Symptoms
Many people become confused when sudden facial weakness occurs. However, there are fundamental differences between seventh nerve paralysis and a stroke:
-
Effect on the forehead muscles: In seventh cranial nerve inflammation, the entire half of the face, including the forehead, is affected. The patient cannot raise the eyebrow on the affected side or wrinkle the forehead. In a stroke, the patient can generally move the forehead and raise the eyebrows normally because the upper facial muscles receive signals from both sides of the brain.
-
Associated symptoms in the body: The effect of seventh nerve inflammation is usually limited to the face, ear, and surrounding tissues, without affecting movement of the rest of the body. In contrast, a stroke is associated with widespread symptoms such as weakness or heaviness in the arm or leg on the same side, noticeably slurred speech, and difficulty with balance or vision.
-
Onset of symptoms: A stroke begins suddenly within a matter of seconds, whereas facial inflammation may be preceded by gradual discomfort lasting from several hours to two days, including symptoms of the seventh cranial nerve before it occurs, such as pain behind the ear and slight deviation of the mouth.
Do Symptoms of the Seventh Cranial Nerve Before It Occurs Require Emergency Care?
Although Bell’s palsy, or facial nerve inflammation, is not usually classified as a life-threatening medical condition, going urgently to the emergency room or neurology department when early symptoms are felt is extremely important. The main danger lies in the strong similarity between temporary facial paralysis and the initial symptoms of a stroke or a sudden cerebral clot, which requires immediate medical evaluation to rule out critical conditions. In addition, rapid attention and an immediate response upon noticing symptoms of the seventh cranial nerve before it occurs—such as severe pain extending behind the ear or sudden numbness on one side of the face—allow the medical team to begin the appropriate treatment protocol (such as corticosteroids) during the golden window (the first 48 to 72 hours). This can greatly increase the likelihood of complete recovery and reduce the chances of permanent complications.
Treatment of the Seventh Cranial Nerve with Professor Dr. Ramadan Shams El-Din
Treatment of facial nerve inflammation under the supervision of Professor Dr. Ramadan Shams El-Din is based on a comprehensive plan specifically designed to suit the degree of nerve injury and the patient’s health status. It includes the following areas:
-
Early medication: Immediate initiation of steroidal anti-inflammatory medication (corticosteroids) to reduce swelling and pressure on the nerve inside the bony canal, with antivirals added in cases where an active viral infection is suspected.
-
Physical-therapy and rehabilitation sessions: Developing a specialized rehabilitation program involving facial exercises and gradual muscle stimulation to ensure the restoration of flexibility and prevent muscle contractions or incorrect synkinesis during recovery.
-
Preventive eye care: Protecting the cornea from dryness by prescribing moisturizing drops during the day and ointments and magnesium at night, while gently closing the eye to prevent ulcers that could affect vision.
-
Follow-up and advanced diagnosis: Using modern examination techniques and nerve studies to assess the extent of nerve-fiber regeneration, especially for those who noticed symptoms of the seventh cranial nerve before it occurred and sought treatment in the early stages.
Frequently Asked Questions About Symptoms of the Seventh Cranial Nerve Before It Occurs
Is the Seventh Cranial Nerve Caused by Emotional Distress?
Yes. Severe stress and psychological pressure may be sufficient to weaken the immune system and trigger nerve inflammation, causing symptoms of the seventh cranial nerve before it occurs, such as pain behind the ear.
How Can I Protect Myself from Seventh Nerve Inflammation?
Avoid sudden, direct exposure to cold drafts, manage psychological stress, and keep blood sugar levels under control.
Can Nerve Inflammation Cause Shortness of Breath?
Seventh cranial nerve inflammation usually does not cause shortness of breath because it affects the facial muscles. However, some widespread peripheral nerve inflammations or severe accompanying stress may cause this sensation.
What Is the First Aid for Seventh Nerve Inflammation?
See a doctor immediately to begin anti-inflammatory treatment within the first 72 hours, protect the affected eye with moisturizing drops, and gently cover it to prevent dryness.
هل التهاب العصب الخامس خطير
Is trigeminal nerve inflammation dangerous? This is one of the most frequently asked questions among patients who suffer from sudden, severe facial pain. Medically, trigeminal neuralgia is classified as one of the most intense forms of neuropathic pain.
The condition appears as severe attacks resembling electric shocks on one side of the face, making simple daily activities such as eating and speaking extremely painful. It directly affects quality of life and raises ongoing concerns about its long-term complications.
In this comprehensive article, we review the causes, symptoms, and diagnostic methods of the condition, while highlighting the leading role of Professor Dr. Ramadan Shams El-Din in providing the latest medical and surgical treatment solutions that restore patients’ comfort and quality of life.
Is Trigeminal Nerve Inflammation Dangerous?
Is trigeminal nerve inflammation dangerous? This inflammation is not usually classified as a condition that directly threatens the patient’s life. However, it is considered serious because of its significant impact on daily quality of life due to the severe and unpredictable facial pain it causes.
The real danger lies in delaying an accurate diagnosis and early treatment. Recurrent attacks can lead to persistent nervous tension and difficulty performing essential tasks such as eating or brushing the teeth.
Managing this condition requires careful follow-up under the supervision of Professor Dr. Ramadan Shams El-Din to determine the extent of nerve involvement and develop an appropriate treatment plan that ensures pain control and prevents worsening.
Symptoms of Trigeminal Nerve Inflammation
Is trigeminal nerve inflammation dangerous when its sudden symptoms are noticed? Symptoms usually appear as sudden, intense attacks of pain resembling an electric shock or a sharp stabbing sensation on one side of the face. They may last from a few seconds to several minutes.
The associated signs vary according to the severity of the condition and the affected nerve branch. The most prominent include:
-
Severe, sudden pain: Concentrated in the jaw, cheek, lips, gums, around the eye, or in the forehead.
-
Pain triggered by the slightest movement: Such as touching the face, shaving, washing the face, eating, or even exposure to cold air.
-
Involuntary muscle contractions: Mild spasms in the facial muscles during a pain attack.
-
Prolonged and recurrent attacks: Attacks may recur for several days or weeks, followed by temporary pain-free periods.
Causes of Trigeminal Nerve Inflammation
The question of whether trigeminal nerve inflammation is dangerous is closely related to the pressure placed on the fifth cranial nerve, which carries sensory signals from the face to the brain. The condition may involve deterioration of the nerve’s protective myelin sheath.
The factors and causes leading to this nerve irritation vary and include the following:
-
Blood-vessel compression: An artery or vein may come into contact with the nerve at the base of the brain, causing continuous pressure and irritation of the nerve fibers.
-
Multiple sclerosis (MS): Damage to the myelin sheath resulting from autoimmune causes.
-
Tumors or cysts: Growths that compress the course of the nerve inside the skull.
-
Advancing age: The likelihood of blood vessels coming into contact with nerves increases with age.
Professor Dr. Ramadan Shams El-Din emphasizes the importance of accurate diagnosis to distinguish vascular causes from other causes and ensure the selection of the most appropriate treatment protocol.
What Factors May Trigger Trigeminal Neuralgia Attacks?
Some simple daily activities can trigger attacks of pain. Patients may wonder whether trigeminal nerve inflammation is dangerous when these sudden pains are triggered by the slightest touch. This extreme sensitivity results from irritation of the nerve fibers and damage to the myelin sheath surrounding them.
The triggers that may cause electrical pain signals in the face include:
-
Light facial touch: Such as washing the face, applying cosmetics, shaving, or drying the face with a towel.
-
Eating and drinking: Chewing, swallowing, or consuming very hot or very cold beverages.
-
Mouth movements and speaking: Talking, smiling, or brushing the teeth.
-
Air exposure: Exposure to a cold draft or sudden wind blowing across the face.
Can Trigeminal Nerve Inflammation Affect Only One Side?
Many patients ask whether trigeminal nerve inflammation is dangerous when severe pain is concentrated on only one side of the face. Medical studies show that the condition does in fact affect only one side—the right or left—in more than 95% of cases.
This localization results from vascular compression or nerve damage affecting one branch of the fifth cranial nerve on one side of the skull. The condition rarely affects both sides simultaneously. When it does, the cause is often related to an immune disorder such as multiple sclerosis.
Professor Dr. Ramadan Shams El-Din explains that accurately identifying the affected side and nerve branch helps in selecting the most appropriate treatment technique, whether through specific medications or precise interventions designed to interrupt painful signals.
What Is the Difference Between Trigeminal Nerve Inflammation and Facial Pain Caused by Other Conditions?
Many patients wonder whether trigeminal nerve inflammation is dangerous compared with other causes of severe facial pain, such as toothache or temporomandibular-joint problems. The essential difference lies in the nature of the pain and its sudden pattern of occurrence.
Trigeminal nerve pain is characterized by brief attacks resembling electric shocks that last for seconds and are triggered by touching the face. In contrast, dental and joint pain is usually continuous, throbbing, or dull and worsens with direct pressure or use.
Professor Dr. Ramadan Shams El-Din relies on a careful clinical examination and magnetic resonance imaging to distinguish nerve pain from other types of pain and ensure proper treatment guidance.
When Does Trigeminal Nerve Inflammation Become More Serious?
Patients often worry about whether trigeminal nerve inflammation is dangerous enough to require immediate intervention. The condition becomes more serious when attacks intensify and become continuous, without intervals of relief.
The seriousness of the situation becomes clear when several factors and complications arise that directly affect the patient’s well-being:
-
Refusal to eat or drink: Fear of triggering pain while chewing may lead to dehydration, malnutrition, and severe weight loss.
-
Neglect of personal and dental hygiene: Avoiding face washing or tooth brushing can cause gum infections and additional health problems.
-
Isolation and sleep disturbances: Repeatedly waking up because of severe pain leads to significant physical and psychological exhaustion.
-
Effect on the optic nerve or cornea: This may occur if the ophthalmic branch of the trigeminal nerve is affected and corneal sensation is lost.
Is Trigeminal Nerve Inflammation Dangerous? Complications of Neglecting Treatment
Patients may ask whether trigeminal nerve inflammation is dangerous when appropriate medical care is neglected. Leaving the condition untreated can lead to complex physical and psychological complications that go beyond temporary pain.
The risks and complications of delaying treatment include:
-
Pain becoming a persistent chronic condition: Increasingly severe and frequent daily attacks may prevent the patient from performing normal activities.
-
Severe weight loss and dehydration: Fear of triggering pain while using the jaw may lead the patient to stop eating and drinking.
-
Damage to oral and dental health: Avoiding tooth brushing or face washing causes bacterial buildup and severe gum inflammation.
-
Loss of corneal sensation: If the ophthalmic branch is affected, the eye may become vulnerable to dryness and corneal ulcers without the patient noticing.
Professor Dr. Ramadan Shams El-Din provides comprehensive treatment programs aimed at containing these complications and restoring full control over the patient’s health and quality of life.
Can Trigeminal Nerve Inflammation Be Treated?
Many patients ask whether trigeminal nerve inflammation is dangerous and whether there are genuine chances of recovery. The answer is yes: the condition can be effectively controlled and treated through several options suited to each individual case.
A comprehensive treatment protocol is available, beginning with conservative and medical solutions and progressing to advanced technical and surgical interventions under the supervision of Professor Dr. Ramadan Shams El-Din. The choice depends on the severity of the attacks and the patient’s response to treatment.
Medication for Trigeminal Nerve Inflammation
Medication is the first and primary option for controlling painful nerve signals and reducing excessive nerve sensitivity. It may include:
-
Anticonvulsants: Such as carbamazepine or oxcarbazepine, which are among the most effective medications for stopping pain signals.
-
Muscle relaxants: Used to relieve muscle contractions associated with severe pain attacks.
-
Specialized nerve-pain medications: Prescribed to reduce nerve irritation and the intensity of sudden attacks.
Non-Surgical Procedures for Treating Trigeminal Nerve Inflammation
When medication becomes less effective or undesirable side effects occur, limited non-surgical techniques may be considered, including:
-
Radiofrequency ablation: Exposing the nerve roots to controlled temperatures to precisely interrupt the transmission of pain signals.
-
Glycerol or alcohol injections: Blocking irritated nerve fibers by injecting soothing substances around the affected nerve.
-
Botox injections: Used in some cases to reduce nerve signals and facial muscle tension.
Surgical Options for Treating Trigeminal Nerve Inflammation
Surgery is a final and effective option for resistant cases or cases caused by direct vascular compression. Options include:
-
Microvascular decompression (MVD): Moving the artery or vein compressing the nerve and placing a medical cushion between them to prevent irritation.
-
Radiosurgery (Gamma Knife): Directing a focused radiation beam at the nerve root to stop the transmission of pain signals without the need for open surgery.
How Is Trigeminal Nerve Inflammation Diagnosed?
Accurate medical evaluation begins by assessing whether trigeminal nerve inflammation is dangerous and determining its effect on the patient through a detailed medical history and a precise description of the pain attacks and their characteristics.
The established diagnostic steps for identifying the underlying cause of facial pain include:
-
Clinical and neurological examination: Examining the branches of the trigeminal nerve and identifying the areas that trigger attacks when touched.
-
Magnetic resonance imaging (MRI): Ruling out tumors and multiple sclerosis and identifying possible vascular compression of the nerve root by an artery.
-
Differential diagnosis: Distinguishing trigeminal nerve pain from dental problems, sinus infections, and temporomandibular-joint disorders.
Professor Dr. Ramadan Shams El-Din ensures that these examinations are performed using modern diagnostic methods to develop the safest and most effective treatment plan.
Can Trigeminal Nerve Inflammation Be Cured?
Many patients ask whether trigeminal nerve inflammation is dangerous and whether it can be eliminated completely. The good news is that complete recovery and full control of symptoms are highly possible thanks to modern medical advances.
The chances of full recovery depend on the primary cause of the condition and how quickly medical intervention begins. Medical treatments and modern techniques can stop the attacks and help the patient return to normal life through:
-
Ongoing medical control: Providing a high rate of symptom control and recovery for most patients in the early stages.
-
Recovery through precise interventions: Techniques such as radiofrequency treatment or microvascular decompression offer excellent results and a high rate of long-term recovery.
-
Removal of the underlying cause: When vascular compression or a mass compressing the nerve is treated, the pain signals may stop completely.
Professor Dr. Ramadan Shams El-Din confirms that early diagnosis and adherence to the treatment plan are the primary keys to achieving the highest recovery rates and preventing relapses.
Does Trigeminal Nerve Inflammation Go Away Without Treatment?
Many people ask whether trigeminal nerve inflammation is dangerous and whether its severe attacks can disappear on their own without medical intervention. Scientific evidence confirms that trigeminal nerve inflammation does not disappear permanently on its own.
The patient may experience temporary periods of remission during which the attacks stop for weeks or months. However, the condition remains present and often returns with attacks that are more severe and frequent if the underlying cause is not addressed.
Professor Dr. Ramadan Shams El-Din warns against relying on these temporary periods of inactivity and recommends starting treatment immediately to prevent deterioration of the nerve and avoid chronic complications.
Tips for Managing Trigeminal Nerve Inflammation
Certain daily practices can reduce the triggering and severity of pain attacks, especially for those wondering whether trigeminal nerve inflammation is dangerous and how common triggers can be avoided.
The most important daily recommendations include:
-
Avoid direct facial triggers: Do not wash the face with extremely cold or hot water; use water at a moderate temperature.
-
Be gentle when brushing the teeth: Use a very soft toothbrush and clean the mouth gently to avoid irritating the nerve branches.
-
Protect the face from air currents: Avoid direct exposure to cold air or air conditioning, and wear a scarf to protect the face in windy weather.
-
Eat foods that are easy to chew: Choose soft and mashed meals to reduce pressure on the jaw and facial muscles during attacks.
-
Avoid nervous stress: Practice relaxation techniques and stay away from psychological stress, which may increase nerve sensitivity.
Can a Person Live with Trigeminal Nerve Inflammation?
Many patients seek an answer to whether trigeminal nerve inflammation is dangerous and whether they can adapt to it in chronic cases. The answer is yes: a person can live a stable and manageable life with this condition by following a healthy lifestyle and a well-regulated treatment plan.
Successful management requires combining medical treatment with simple behavioral modifications that protect the face from daily triggers and prevent the activation of painful nerve signals.
The most important aspects of living well with the condition include:
-
Strict adherence to medication doses: Do not stop or change the dose of nerve-pain medication without consulting a doctor, in order to prevent the attacks from returning.
-
Dietary modifications: Choose soft, easily digestible foods and consume them at moderate temperatures to avoid triggering pain.
-
Psychological support and relaxation: Reduce stress and psychological pressure, which can increase nervous-system sensitivity.
When Should You Consult a Doctor Because of Trigeminal Nerve Inflammation?
Patients often worry about whether trigeminal nerve inflammation is dangerous and what symptoms require an immediate clinic visit. Medical evaluation should be sought when sudden, severe facial pain appears and does not respond to ordinary painkillers.
The following signs and circumstances require urgent medical consultation without delay:
-
Sudden, severe facial pain: Pain resembling an electric shock that recurs while eating or speaking.
-
Current medication is ineffective: Attacks become more severe or frequent despite adhering to the prescribed treatment.
-
Difficulty eating or drinking: Inability to consume food or liquids, which creates a risk of dehydration and malnutrition.
-
Severe side effects: Such as intense dizziness or impaired movement resulting from medication.
Professor Dr. Ramadan Shams El-Din provides specialized consultations and comprehensive examinations to develop an integrated treatment plan that ensures complete pain control and restores comfort to your life.
هل التهاب العصب السابع خطير؟
Is seventh cranial nerve inflammation dangerous? This is one of the first concerns that comes to patients’ minds when they suddenly notice a change in the shape of the face or unexpected drooping on one side. This disorder is medically known as Bell’s palsy and results from irritation or inflammation of the nerve responsible for controlling the facial muscles of expression.
The condition causes noticeable drooping of the lips, difficulty closing the eye, and changes in normal facial expressions. This often raises significant concern about whether it may be linked to serious problems such as a stroke. These sudden changes affect the patient psychologically and alter their overall appearance, leading them to seek a clear understanding of the condition’s seriousness and possible complications.
In this comprehensive article, we review the causes and symptoms of this nerve irritation and explain how to distinguish it from strokes, while highlighting the leading role of Professor Dr. Ramadan Shams El-Din in providing the latest medical and physical-therapy solutions to achieve complete recovery and restore normal facial symmetry.
Is Seventh Cranial Nerve Inflammation Dangerous?
Is seventh cranial nerve inflammation dangerous? Overall, this inflammation is not considered life-threatening or dangerous. Most patients recover completely and regain normal facial-muscle function within a few weeks or several months after treatment begins.
The real danger lies in the possibility of lasting eye complications caused by the inability to close the eye, or in delaying early medical treatment during the first days after symptoms appear. This may slow the nerve’s recovery and reduce its response to treatment.
Managing this condition requires careful medical follow-up with Professor Dr. Ramadan Shams El-Din to assess the degree of motor impairment and establish an integrated treatment protocol that protects the eye and accelerates the restoration of facial balance.
What Is Seventh Cranial Nerve Inflammation?
Is seventh cranial nerve inflammation dangerous once its medical nature is understood? This condition is known as Bell’s palsy. It is swelling or inflammation affecting the seventh cranial nerve, which controls movement and the muscles responsible for facial expressions on one side of the face.
This irritation causes sudden weakness or temporary paralysis, making it difficult to close the eye, smile, or control lip movement symmetrically. As a result, the features of the affected side change noticeably.
Professor Dr. Ramadan Shams El-Din explains that the seventh cranial nerve passes through a narrow bony canal in the skull. When it becomes inflamed, it swells and is compressed within this passage, preventing motor signals from traveling from the brain to the facial muscles.
Symptoms of Seventh Cranial Nerve Inflammation
Is seventh cranial nerve inflammation dangerous when its first signs appear? Symptoms usually develop suddenly, often within 24 to 48 hours. The patient notices motor weakness or complete drooping on one side of the face without prior warning.
The associated signs vary and directly affect facial functions and everyday expressions. The most prominent include:
-
Difficulty closing the eye and eye dryness: The inability to close the eyelid completely on the affected side exposes the eye to dryness and irritation.
-
Drooping of the corner of the mouth: The lip falls, making it difficult to smile or control liquids and prevent them from leaking.
-
Pain behind the ear or in the jaw: A vague ache or discomfort around the ear may precede or accompany muscle weakness.
-
Changes in taste and increased sensitivity to sounds: Loss of taste in the front part of the tongue and increased discomfort from loud sounds.
Professor Dr. Ramadan Shams El-Din stresses the importance of rapid diagnosis as soon as these symptoms are noticed to ensure early treatment and achieve the highest possible recovery rates.
When Does Seventh Cranial Nerve Inflammation Become Dangerous?
The question of whether seventh cranial nerve inflammation is dangerous and when it requires emergency medical attention arises repeatedly. The condition becomes more serious when medical care is neglected during the first days or when severe damage to the nerve fibers makes muscle recovery more difficult.
The real danger appears and requires immediate intervention in several situations and major complications:
-
Impaired eye and eyelid health: Complete inability to close the eye can cause severe corneal dryness, corneal ulceration, and a possible partial loss of vision.
-
Neglecting early steroid treatment: Delaying anti-inflammatory medication during the first 72 hours significantly reduces the chances of complete recovery.
-
Permanent facial paralysis: Persistent muscle weakness and atrophy without improvement several months after the injury.
-
Abnormal synkinesis: Irregular nerve regrowth that causes the eye to contract or close when the patient smiles.
Professor Dr. Ramadan Shams El-Din ensures prompt and regular follow-up for these cases to avoid such risks and protect the eye from lasting damage.
Complications of Neglecting Treatment for Seventh Cranial Nerve Inflammation
Patients often ask whether seventh cranial nerve inflammation is dangerous when treatment is ignored. Neglecting prompt medical intervention can lead to permanent nerve damage and a noticeable decline in the effectiveness of facial expressions.
The complications resulting from neglecting the condition include:
-
Irreversible facial-nerve damage: Permanent atrophy of nerve fibers that prevents the complete restoration of normal movement.
-
Irregular nerve regrowth (synkinesis): Involuntary contraction of the facial muscles, such as automatic eye closure when smiling.
-
Corneal ulceration and severe dryness: Damage to the surface of the eye resulting from the continued inability to close the eyelid and provide adequate moisture.
-
Shortening and contraction of the facial muscles: Permanent shortening of the muscles on the affected side, causing obvious facial asymmetry.
Does Seventh Cranial Nerve Inflammation Cause Permanent Paralysis?
Many people worry about whether seventh cranial nerve inflammation is dangerous and whether it can end in permanent facial paralysis. In reality, the vast majority of cases recover completely, and permanent paralysis occurs only in a very small percentage of patients.
Permanent paralysis is associated with complete damage to the nerve fibers or severe injury at the origin of the nerve that did not receive early and appropriate treatment with steroids and neurotrophic medications during the first days.
Professor Dr. Ramadan Shams El-Din recommends that patients undergo medical evaluation promptly and begin physical therapy and anti-inflammatory medication to prevent reaching this critical stage and to ensure muscle recovery.
Does Seventh Cranial Nerve Inflammation Affect the Eye?
Patients’ concerns about whether seventh cranial nerve inflammation is dangerous and how it directly affects the eye continue to increase. The eye is the part most affected by the condition because control over the muscles surrounding the eyelid is lost.
Nerve weakness prevents the eyelid from fully covering the eye, resulting in several visual and health problems:
-
Severe dryness and irritation: Tears evaporate quickly because the eye remains open for long periods.
-
Exposure to infection and dust: The absence of natural coverage leaves the cornea vulnerable to bacteria and external scratches.
-
Blurred vision: Temporary visual blurring may occur because of dryness on the eye’s outer surface.
Does Seventh Cranial Nerve Inflammation Affect the Brain?
Some people wonder whether seventh cranial nerve inflammation is dangerous and whether its effects can extend to the brain. Medical evidence confirms that it is an isolated peripheral condition and does not affect brain cells or cognitive functions.
The inflammation is limited to the seventh cranial nerve outside the brain tissue as it passes through its bony pathway in the skull. Therefore, it does not cause brain atrophy, memory loss, or concentration problems.
Professor Dr. Ramadan Shams El-Din reassures patients that this disorder is not a central brain disease. Rather, it is a temporary peripheral dysfunction affecting the nerve responsible only for facial expressions and movement.
Difference Between Seventh Cranial Nerve Inflammation and Stroke
Patients frequently have serious concerns about whether seventh cranial nerve inflammation is dangerous and whether it is a sign of a stroke. Although the two conditions may appear similar because both can involve facial drooping, there is a fundamental medical difference between them.
The two conditions can be distinguished by examining the nature of the motor impairment and the affected facial muscles:
-
Involvement of the forehead and eyebrow: Seventh cranial nerve inflammation affects the entire half of the face, including the forehead, whereas a stroke usually preserves movement of the forehead.
-
Associated physical symptoms: Seventh cranial nerve inflammation is limited to the face, while a stroke is accompanied by weakness or heaviness in the arm and leg and slurred speech.
-
Nature of the underlying problem: Seventh cranial nerve inflammation is a peripheral facial-nerve disorder, whereas a stroke is a central disorder caused by reduced blood flow to the brain.
Causes of Seventh Cranial Nerve Inflammation
Many people ask whether seventh cranial nerve inflammation is dangerous when considering its causes. The condition is usually attributed to an immune response or reactivation of a previous viral infection, which causes the nerve to swell and become compressed within its narrow pathway.
The causes and factors leading to irritation of this facial nerve include:
-
Common viral infections: Such as herpes simplex virus, varicella-zoster virus (shingles), and influenza and common-cold viruses.
-
Sudden exposure to air currents: Rapid movement from a warm environment into very cold air, which may cause spasms in the blood vessels supplying the nerve.
-
Weakened immunity and psychological stress: Severe physical exhaustion and ongoing psychological stress reduce the body’s resistance and may reactivate dormant viruses.
-
Hormonal changes and pregnancy: The incidence may increase in women during the final months of pregnancy or immediately after childbirth.
How Is Seventh Cranial Nerve Inflammation Diagnosed?
Accurate medical evaluation begins by assessing whether seventh cranial nerve inflammation is dangerous and determining the extent of nerve-fiber involvement. This is done through a comprehensive clinical examination and observation of facial-muscle movement and different expressions.
The established diagnostic steps include:
-
Clinical neurological examination: Smiling, closing the eyes tightly, and raising the eyebrows to assess the degree of weakness and determine whether the entire nerve is affected.
-
Imaging tests (magnetic resonance imaging, MRI): Ruling out other central causes, such as tumors or bony compression of the nerve.
-
Electromyography and nerve testing (EMG): Assessing the extent of nerve-fiber damage and determining the likelihood and speed of future recovery.
Can Seventh Cranial Nerve Inflammation Be Treated?
Many patients ask whether seventh cranial nerve inflammation is dangerous and whether there are genuine chances of recovery. The answer is yes: the condition can be treated very effectively, and full facial function can be restored when treatment begins early.
The treatment plan combines medication with physical therapy to protect the nerve and activate movement:
-
Corticosteroids and anti-inflammatory medications: Given during the first 72 hours to reduce swelling of the nerve inside the bony canal and accelerate recovery.
-
Antiviral medications: Used in some cases associated with an active viral infection to reduce the severity of the condition.
-
Physical therapy and motor rehabilitation: Customized exercises and therapy sessions to stimulate the muscles and prevent contraction while the nerve regains strength.
When Do Signs of Seventh Cranial Nerve Improvement Appear?
Patients continually seek an answer to whether seventh cranial nerve inflammation is dangerous and when the face will begin to regain its natural features. Improvement generally begins within two to three weeks after the condition starts, provided the patient follows the treatment plan.
The stages of recovery vary according to the degree of nerve damage and the level of early care provided:
-
Early improvement (2–3 weeks): The ability to control the corner of the mouth begins to return, and eye dryness decreases.
-
Intermediate recovery (1–3 months): Motor balance returns to most facial muscles and the smile becomes more responsive.
-
Comprehensive recovery (up to 6 months): Full movement and coordinated facial expressions return in moderate to severe cases.
Does Seventh Cranial Nerve Inflammation Disappear Without Treatment?
Many people ask whether seventh cranial nerve inflammation is dangerous and whether weakness can disappear on its own without medication. Some mild cases may improve spontaneously, but leaving the condition untreated increases the risks.
Failing to receive early treatment prolongs the recovery period and increases the likelihood of permanent complications, such as partial paralysis or asymmetrical muscle stiffness.
Professor Dr. Ramadan Shams El-Din recommends starting anti-inflammatory treatment and physical therapy immediately to protect the nerve fibers and achieve the highest possible recovery rate without lasting complications.
Can Seventh Cranial Nerve Inflammation Be Prevented?
Many people wonder whether seventh cranial nerve inflammation is dangerous and whether it can be prevented. There is no guaranteed way to prevent it completely because it may be associated with sudden viral reactivation. However, there are recommendations that can reduce the risk.
Certain healthy habits help support nerve health and reduce the likelihood of inflammation:
-
Avoid sudden temperature changes: Avoid direct exposure to cold drafts after being in a warm environment.
-
Support immune health: Follow a balanced, vitamin-rich diet, especially one containing B vitamins that support nerve health.
-
Manage stress and exhaustion: Reduce psychological and physical stress, which may weaken the immune system and reactivate dormant viruses.
-
Control chronic diseases: Monitor blood sugar regularly to avoid diabetic neuropathy.
When Should You Consult a Doctor for Seventh Cranial Nerve Inflammation?
Patients frequently ask whether seventh cranial nerve inflammation is dangerous and when the condition requires urgent medical evaluation. It is best to consult a doctor immediately if any sudden weakness or change in facial expression occurs.
The following symptoms require an immediate visit to a medical clinic to ensure that treatment begins at the ideal time:
-
Sudden facial drooping: Difficulty smiling or unexpected drooping of one corner of the mouth developing within hours.
-
Difficulty fully closing the eyelid: Severe dryness or sharp stinging in the eye because the eyelid cannot cover it.
-
Severe pain behind the ear: Discomfort that precedes muscle weakness or accompanies drooping of the lip.
-
A change in taste: Loss of taste in the front part of the tongue accompanied by excessive sensitivity to sounds.
Treatment of Seventh Cranial Nerve Inflammation with Professor Dr. Ramadan Shams El-Din
Is seventh cranial nerve inflammation dangerous when managed by a specialist? Optimal and safe treatment is available under the supervision of Professor Dr. Ramadan Shams El-Din through an integrated treatment plan based on a careful assessment of the extent of nerve involvement.
The treatment protocol combines modern therapies to ensure complete restoration of movement and avoid lasting complications:
-
Early medication protocol: Prescribing precise doses of corticosteroids and antiviral medications to reduce swelling of the nerve within its bony pathway.
-
Eye protection and care: Providing the necessary eye drops and moisturizers, along with protective dressings to shield the eye from dryness and ulceration during sleep.
-
Specialized rehabilitation and physical therapy: Guided exercise sessions to stimulate the muscles and effectively restore coordinated facial expressions.
Book your consultation now and regain your facial balance and smile. Do not hesitate to begin your recovery journey early. To contact Professor Dr. Ramadan Shams El-Din’s clinic directly and schedule an appointment, contact us immediately via WhatsApp to receive the medical care most appropriate for your condition.
علاج التهاب عصب الرجل اليسرى
The treatment of left-leg nerve inflammation is one of the most searched and discussed medical topics among people who experience sudden or radiating pain that begins in the lower back and extends along the left leg. This condition is commonly referred to as sciatica or peripheral neuropathy and is usually caused by compression or irritation of the sciatic nerve on the left side of the body.
This irritation causes an uncomfortable sensation of heat, numbness, or sharp pain that interferes with the ability to walk and sit normally, directly affecting quality of life and daily activities. These sudden sensations cause patients concern and lead them to search for the latest medical methods and effective non-surgical solutions for controlling and eliminating the pain.
In this comprehensive article, we review all the details related to the condition, its causes, and accurate diagnostic methods, while highlighting the leading role of Professor Dr. Ramadan Shams El-Din in providing the latest treatment options and advanced rehabilitation protocols to achieve complete recovery.
What Is Left-Leg Nerve Inflammation?
Left-leg nerve inflammation refers to irritation or compression affecting the sciatic nerve or the peripheral nerve fibers extending along the left lower limb.
This irritation disrupts the transmission of nerve signals from the lower back and sacral vertebrae down to the leg and foot, causing sharp pain, numbness, or a burning sensation extending along the leg.
Professor Dr. Ramadan Shams El-Din explains that this condition is most often caused by a spinal disc herniation or narrowing of the spinal canal. This requires an accurate diagnostic assessment to identify the source of compression and determine the appropriate treatment.
#call#
Treatment Methods for Left-Leg Nerve Inflammation
Treatment options for left-leg nerve inflammation vary according to the severity of pressure on the affected nerve and the patient’s response to conservative care. The primary goals are to reduce pain, control inflammation, and restore the patient’s ability to move normally without pain.
Available treatment options include medication, physical therapy, and advanced interventions, as detailed below.
Medication for Left-Leg Nerve Inflammation
The medication plan relies on a comprehensive combination of drugs to reduce swelling around the nerve roots. Nonsteroidal anti-inflammatory drugs may be used to control severe pain, together with specialized nerve-pain medications that calm abnormal nerve signals. The doctor may also prescribe muscle relaxants to relieve spasms around the lower back, along with B-complex vitamins to support nerve regeneration.
Physical Therapy and Motor Rehabilitation
Physical therapy plays a central role in reducing mechanical pressure on the sciatic nerve through carefully designed rehabilitation programs. Sessions may include electrical nerve stimulation, heat therapy, and compresses to reduce spasms. Movement modification and therapeutic massage also help improve blood flow to the affected nerves and significantly reduce tension in the muscles surrounding the lumbar vertebrae.
Appropriate Exercises for Treating Left-Leg Nerve Inflammation
Stretching and physical-rehabilitation exercises help strengthen the muscles that support the spine and reduce pressure on the leg nerve. The main exercises include piriformis stretching and hamstring stretching, which improve leg flexibility. These exercises should preferably be performed gradually and under the supervision of a specialist to avoid excessive strain, with a focus on pelvic-stability exercises to ensure balanced weight distribution while walking.
Injections for Left-Leg Nerve Inflammation
Local injections are an advanced and effective option for cases that do not respond to traditional oral and conservative treatments. An anti-inflammatory corticosteroid may be injected directly around the affected nerve roots using precise image-guided interventional techniques. This method helps reduce nerve swelling and relieve pain for extended periods, giving the patient an excellent opportunity to continue physical therapy without pain.
Surgery for Left-Leg Nerve Inflammation
Surgery is considered the final option when there is advanced nerve damage or motor weakness in the foot. Techniques include removing a herniated disc that is compressing the nerve or widening a narrowed spinal canal in the lower back. These procedures are now performed using microsurgery or advanced endoscopic techniques to minimize surgical intervention, ensure rapid recovery, and help the patient return to normal life.
#call#
Symptoms of Left-Leg Nerve Inflammation
There are several signs and symptoms that may lead a person to seek treatment for left-leg nerve inflammation. The patient may experience symptoms of varying severity that usually begin in the lumbar region of the lower back and travel down the left lower limb.
These symptoms directly affect daily quality of life and include:
-
Sharp, shooting pain: Pain resembling an electric shock or a sharp stab that begins in the buttocks and travels down the back of the thigh and leg.
-
Burning and heat sensation: A painful internal burning sensation extending along the course of the sciatic nerve in the left leg, often worsening with sneezing or coughing.
-
Persistent numbness and tingling: Partial loss of sensation or a constant pins-and-needles sensation in the left leg, ankle, or toes.
-
Muscle weakness and difficulty moving: Difficulty moving the affected leg or weakness when lifting the foot off the ground while walking (foot drop).
-
Pain aggravated by certain positions: A noticeable increase in symptoms when sitting for long periods, standing up suddenly, or bending the torso forward.
-
Associated lower-back pain: Stiffness and pain extending through the lumbar and sacral vertebrae, preceding or accompanying pain in the left leg.
Causes of Left-Leg Nerve Inflammation
Effective treatment of left-leg nerve inflammation requires a precise understanding of the organic and anatomical causes that irritate the sciatic nerve or its roots on the left side of the body. In most cases, the inflammation results from direct mechanical pressure on the nerve fibers as they exit the lumbar spine and pass through the pelvis toward the lower limb.
The causes and factors leading to irritation of the left-leg nerve include:
-
Lumbar disc herniation: The most common cause. The gelatinous portion of a disc between the lumbar vertebrae—particularly between L4–L5 or L5–S1—protrudes and directly compresses the nerve root traveling toward the left leg.
-
Spinal stenosis: Degenerative changes and aging may narrow the bony passages through which the nerves travel, causing continuous pressure on the sciatic nerve that worsens while walking or standing.
-
Piriformis syndrome: Spasm or enlargement of the piriformis muscle in the buttocks compresses the sciatic nerve, which passes directly beneath it, causing sharp pain that radiates down the left leg.
-
Spondylolisthesis: One lumbar vertebra moves out of its normal position and slips over the vertebra below it, narrowing the neural foramen and placing severe pressure on the nerve fibers.
-
Arthritis and bone spurs: Excess bone growth at the edges of the vertebrae caused by spinal-joint inflammation may rub against the nerves and directly inflame them.
-
Lifestyle and physical strain: Incorrect heavy lifting, prolonged sitting in an unhealthy position, and excess weight increase the mechanical load on the lower-back vertebrae.
How Is Left-Leg Nerve Inflammation Diagnosed?
Successful treatment of left-leg nerve inflammation depends on a precise and carefully structured diagnostic plan that distinguishes between the different causes of nerve compression. Medical methods and modern technologies are combined to identify the exact source of inflammation and the extent of damage to the sciatic nerve.
The main diagnostic steps include the following:
Clinical and Neurological Examination
Diagnosis begins with a comprehensive clinical assessment of muscle strength, reflexes, and sensitivity to touch and temperature in different parts of the leg and foot. The doctor may perform the straight-leg-raise test (Lasègue’s test) to assess the nerve’s response to stretching and confirm whether its lumbar roots are irritated.
Spinal Imaging
Imaging studies help reveal structural changes in the lower back. X-rays may show spinal alignment, arthritis, or bone spurs. Magnetic resonance imaging (MRI) is considered the gold standard for accurately diagnosing disc herniation and showing details of the soft tissues and compressed nerves inside the spinal canal.
Nerve and Muscle Studies
Nerve conduction studies and electromyography (EMG/NCS) are used to measure the speed and efficiency of electrical conduction through the nerve fibers extending into the leg. This procedure helps determine the level of nerve damage and distinguish between compression of a nerve root in the lower back and peripheral neuropathy along the leg.
Tips for Relieving Left-Leg Nerve Pain at Home
Daily home care and initial symptom control can support the treatment of left-leg nerve inflammation and reduce acute attacks that interfere with movement. Following healthy practices helps reduce swelling around the sciatic nerve and relieve associated muscle spasms in the lower back and leg.
Important home-care recommendations include:
-
Alternate cold and warm compresses: During the first 48 hours, apply ice packs wrapped in a cloth to the lower back for 15–20 minutes several times a day to reduce inflammation and swelling. Then switch to warm compresses to improve circulation and relax tight muscles.
-
Avoid prolonged bed rest: Resume light activities and short walks as soon as the acute pain improves. Remaining in bed continuously for more than two days weakens the muscles, increases spinal stiffness, and aggravates nerve irritation.
-
Adjust sitting and sleeping positions: Sit on chairs that support the lower back, avoid leaning forward or crossing one leg over the other, and sleep on your side with a pillow between your knees. Alternatively, sleep on your back with a pillow under your knees to reduce direct pressure on the lumbar vertebrae.
-
Avoid lifting heavy objects: Completely avoid carrying heavy items or making sudden bending and twisting movements of the back. Bend your knees and use your leg muscles when picking anything up from the floor.
-
Use medical supports and pillows: Use specially designed lumbar-support pillows while driving or working at a desk to reduce continuous mechanical strain on the affected nerve.
Exercises That May Help Relieve Left-Leg Nerve Inflammation
Carefully planned therapeutic exercises play an effective role in an integrated treatment plan for left-leg nerve inflammation, provided they are performed cautiously and according to the body’s response. These directed movements help release muscle spasms and stretch the tissues surrounding the lumbar vertebrae, making it easier to move the lower limb without severe pain.
The most useful simple home exercises include:
-
Piriformis stretch: Lie on your back with your knees bent. Place the ankle of the affected left leg over the thigh of the right leg, then gently draw the right thigh toward the chest until a mild stretch is felt in the buttocks and left side. Hold for 20 seconds.
-
Single-knee-to-chest stretch: Lie flat on your back with both legs extended. Gradually bend the left knee and gently pull it toward the chest with both hands. Hold for approximately 15 seconds to reduce lower-back muscle tension and stretch the nerve pathway.
-
Gentle lower-back flexion (cat-cow stretch): Get onto your hands and knees. Slowly arch the back upward toward the ceiling while lowering the head, then carefully reverse the movement by lowering the abdomen toward the floor to mobilize the spinal vertebrae.
-
Hamstring and calf stretch: Sit on the edge of a chair with the left leg extended forward and the heel on the floor. Gently bend forward from the hips without rounding the spine until a mild stretch is felt in the back of the left thigh.
Can Left-Leg Nerve Inflammation Be Permanently Treated?
Yes. In most cases, left-leg nerve inflammation can be treated and eliminated completely, particularly when it is detected early and the exact cause of pressure on the sciatic nerve is identified. Complete recovery depends on removing the source of irritation, whether it is a disc herniation, muscle spasm, or narrowing of the neural pathway.
Conservative medication protocols and physical therapy lead to recovery in more than 80% to 90% of patients without the need for surgery. In advanced cases that do not respond to initial solutions, modern interventions such as local injections or precise microsurgery provide excellent results and allow patients to return fully to their normal lives without recurrent pain.
How Long Does Treatment for Left-Leg Nerve Inflammation Take?
The time required to treat left-leg nerve inflammation varies according to the severity of the inflammation, its underlying cause, and the patient’s adherence to medical instructions and recommendations:
-
Mild to moderate cases: Recovery and noticeable improvement generally take 4–6 weeks with relative rest, pain medication, and physical-therapy sessions.
-
Severe or chronic cases: Complete recovery may take 2–3 months, especially when there is significant disc compression requiring intensive strengthening and motor rehabilitation.
-
After surgery or injections: Relief and pain reduction may begin immediately or within a few days of the procedure, while rehabilitation to restore full muscle strength continues for 4–8 weeks.
When Is Left-Leg Nerve Inflammation Dangerous?
Left-leg nerve inflammation is serious and requires urgent medical intervention when signs appear indicating severe, direct pressure that threatens the integrity and blood supply of the nerve fibers.
The condition becomes an emergency requiring immediate evaluation when any of the following signs are noticed:
-
Cauda equina syndrome: Sudden loss of control over urination or bowel movements, or complete numbness in the saddle area between the thighs.
-
Progressive motor weakness or foot drop: Inability to lift the front of the left foot while walking or severe heaviness that prevents the leg from bearing body weight.
-
Complete loss of sensation: Numbness and tingling extending throughout all parts of the leg and foot without relief.
-
Severe pain unresponsive to medication: Persistent, intense pain that worsens even while lying down and resting and completely prevents sleep.
Signs That Require Immediate Medical Consultation
Although most cases of nerve irritation gradually improve with conservative care, certain severe warning signs indicate significant pressure threatening the safety of the nerve tissue. If any of these symptoms appear, the patient should go to a clinic immediately to prevent complications or permanent damage to the nerve fibers extending into the leg.
The most important signs requiring urgent medical examination include:
-
Loss of bladder or bowel control: Sudden urinary incontinence or inability to control bowel movements.
-
Saddle anesthesia: Complete loss of sensation or numbness in the area around the pelvis and between the thighs.
-
Foot drop: Sudden motor weakness that prevents the patient from lifting the front of the left foot or walking on the heels.
-
Spread of motor weakness: Severe weakness and numbness that rapidly extend throughout the left leg and cause stumbling or falls while walking.
-
Severe, constant, unbearable pain: Intense pain that does not improve with bed rest or strong painkillers and completely prevents sleep.
Treatment of Left-Leg Nerve Inflammation with Professor Dr. Ramadan Shams El-Din
Choosing a specialized doctor is the essential step and a guarantee of genuine recovery when seeking treatment for left-leg nerve inflammation. Neurological assessment requires a high degree of precision to identify the direct cause of compression and design a treatment plan tailored to each patient.
Professor Dr. Ramadan Shams El-Din provides an integrated medical approach based on the latest international protocols for treating spinal and neurological diseases and performing related surgeries, with an emphasis on non-surgical solutions and advanced interventional techniques.
Under Professor Dr. Ramadan Shams El-Din’s supervision, medical care includes the following stages:
-
Early and accurate diagnosis: Using advanced clinical examination techniques, careful interpretation of MRI scans, and nerve studies to identify the source of irritation precisely.
-
Non-surgical interventional treatment plans: Applying the latest image-guided focal injection techniques and nerve-root injections to reduce inflammation immediately and minimize the need for traditional surgery.
-
Customized motor-rehabilitation programs: Supervising physical-therapy programs to strengthen the back muscles and fully restore leg flexibility without future relapses.
-
Microsurgical interventions: When surgery is required, using the latest endoscopic and minimally invasive microsurgical techniques to achieve the highest success rates and the fastest possible recovery.
#call#
علاج التهابات الاعصاب الطرفية
Peripheral nerves form the communication network responsible for transmitting signals and sensation between the central nervous system and the various parts of the body. Therefore, any disorder affecting them directly impacts quality of life and the ability to perform daily activities. Many people seek treatment for peripheral neuropathies to get rid of the bothersome pain and persistent numbness affecting the limbs, which may eventually interfere with movement and balance.
Available treatment options vary according to the primary cause of the inflammation and the stage of the condition. Medication and rehabilitation solutions are combined to achieve the best possible results. In this comprehensive article, Professor Dr. Ramadan Shams El-Din reviews the causes and symptoms of this condition, as well as the latest methods and protocols used to treat peripheral neuropathies and restore nerve health and function.
What Are Peripheral Neuropathies?
Peripheral neuropathies are medical conditions resulting from dysfunction or damage to nerve fibers that extend outside the brain and spinal cord. These nerves carry sensory and motor messages between the central nervous system and the rest of the body, including the hands and feet.
This dysfunction disrupts the transmission of nerve signals, causing numbness, tingling, and sharp pain in the limbs. Professor Dr. Ramadan Shams El-Din emphasizes that understanding the nature of this damage is the first step toward determining the appropriate treatment plan, preventing the injury from worsening, and restoring the function of the affected nerves.
#call#
Treatment Methods for Peripheral Neuropathies
Management of peripheral neuropathies requires a comprehensive medical approach aimed at stopping nerve damage, relieving associated pain, and improving the patient’s quality of life. Treatment protocols gradually address the underlying causes, while also using advanced medical and rehabilitation techniques as follows.
Treating the Underlying Cause of Nerve Inflammation
Treating the primary cause is the cornerstone of recovery. Lasting improvement cannot be achieved without fully controlling the initial factor irritating the nerves. This may include carefully controlling blood sugar in patients with diabetes, treating hormonal disorders such as thyroid disease, or discontinuing medications with toxic effects on the nerves in consultation with a specialist to ensure that deterioration of the nerve fibers stops.
Medication
A specialized group of medications is used to reduce bothersome sensory symptoms and control nerve pain. These include nerve-pain medications such as gabapentin and pregabalin, which regulate abnormal nerve signals sent to the brain. Analgesics, nonsteroidal anti-inflammatory drugs, and topical anesthetic creams may also be used to relieve severe burning and tingling during acute episodes.
Physical Therapy and Motor Rehabilitation
Physical therapy plays a strategic role in restoring movement and protecting the muscles from atrophy caused by impaired nerve supply. Sessions include muscle-strengthening exercises and balance training to reduce the risk of falls, in addition to transcutaneous electrical nerve stimulation (TENS), which helps improve peripheral circulation and reduce the intensity of pain signals.
Treating Vitamin and Mineral Deficiencies
This aspect of treatment focuses on correcting nutritional deficiencies that negatively affect the protective myelin sheath around the nerves. Patients may receive intensive doses of B-complex vitamins, particularly vitamins B1, B6, and B12, which play a central role in nerve-cell regeneration and function. Testing and correcting magnesium and vitamin D levels may also be recommended to ensure proper nerve conduction and reduce muscle spasms.
Symptoms of Peripheral Neuropathies
Symptoms resulting from nerve dysfunction vary in type and severity according to the nerve fibers affected and the speed at which the inflammation spreads. Patients may notice sensory and motor signs that usually begin in the upper or lower limbs and directly affect their ability to perform daily activities.
The most common symptoms that lead people to seek treatment for peripheral neuropathies include:
Numbness and Tingling in the Hands or Feet
Numbness and a sensation resembling thousands of pins and needles are among the first signs of irritation of the sensory nerve fibers. These symptoms often begin in the fingers or toes and gradually spread to the forearms or legs in a pattern resembling the wearing of “gloves and socks.” The tingling may become more noticeable during periods of rest or in the evening.
Burning Sensation or Severe Pain
Patients may experience severe burning or stabbing pain resembling repeated electric shocks. Sensitivity to light touch may become so intense that the patient cannot tolerate clothing or bed sheets touching the affected skin. This severe pain results from inflamed peripheral nerves transmitting exaggerated signals to the brain.
Muscle Weakness and Difficulty Moving
Damage to the motor nerve fibers responsible for transmitting movement commands leads to reduced muscle strength in the limbs. This may cause difficulty gripping objects firmly or dropping items from the hands, as well as difficulty climbing stairs or rising from a seated position because of weakness in the feet and leg muscles.
Loss of Sensation or Loss of Balance
Advanced nerve damage reduces the patient’s ability to feel temperature or mechanical pain, exposing the limbs to unnoticed injuries and wounds. The patient may also lose proprioception—the awareness of the position of the limbs in space—which can lead to unsteadiness, stumbling, and loss of balance while walking, especially in dark places.
Causes of Peripheral Neuropathies
Damage to nerve fibers in the limbs may result from a wide range of organic and environmental factors that interfere with the nerve’s blood supply or damage its protective myelin sheath. Identifying the exact cause is an essential step in treating peripheral neuropathies effectively and preventing continued neurological deterioration.
The causes of this condition include:
Diabetes
Diabetic neuropathy is the most common cause. Chronic, poorly controlled high blood sugar damages the small blood vessels that supply the peripheral nerves and leads to the accumulation of toxic substances directly on the nerve fibers. This causes numbness and severe pain that typically begin in the feet.
Vitamin B12 Deficiency
Vitamin B12 plays an essential role in producing the myelin sheath that protects the nerves and ensures rapid electrical conduction. Poor nutrition or problems with gastrointestinal absorption can cause a deficiency, leading to erosion of the protective nerve layer and the appearance of numbness and balance problems.
Nerve Compression and Disc Herniation
Persistent mechanical pressure caused by protruding spinal discs, narrowing of the neural canals, or carpal tunnel syndrome in the hands can restrict normal blood flow to the nerve and irritate it. This results in acute inflammation and pain signals extending along the compressed nerve.
Certain Autoimmune and Inflammatory Diseases
Some types of neuropathy occur when the immune system mistakenly attacks the body’s own nerve tissue, as in Guillain–Barré syndrome, chronic inflammatory demyelinating polyneuropathy (CIDP), systemic lupus erythematosus, and rheumatoid arthritis. These conditions may cause widespread inflammation in the limbs.
Side Effects of Certain Medications
Some medications have direct toxic effects on peripheral nerve fibers. These include chemotherapy drugs used to treat cancer, certain antibiotics and antivirals when taken for long periods, and some medications used to regulate heart rhythm and blood pressure.
How Are Peripheral Neuropathies Diagnosed?
Successful and effective treatment of peripheral neuropathies depends on accurate initial diagnosis to identify the direct cause of the nerve dysfunction and determine which fibers are affected and to what extent. Medical methods and modern technologies are combined to assess peripheral nervous-system function with great precision.
The comprehensive diagnostic process includes:
Neurological Examination
Diagnosis begins with a careful clinical evaluation. The doctor assesses reflexes, muscle strength in the limbs, and nerve responses to different sensory stimuli such as vibration, light touch, pinprick, and temperature. The examination also evaluates balance and the ability to walk steadily to determine the extent to which sensory and balance-related nerve fibers are affected.
Blood Tests
Comprehensive laboratory tests are performed to identify organic and metabolic factors causing nerve inflammation. These may include glycated hemoglobin (HbA1c) to check for diabetes, vitamin B12 and vitamin D levels, liver and kidney function tests, immune-marker tests, and inflammatory markers to assess the possibility of autoimmune disease.
Nerve and Muscle Studies
Nerve conduction studies and electromyography (EMG/NCS) are the standard tests for evaluating nerve function. They measure the speed and strength of electrical signals traveling through the nerve fibers. These tests help distinguish damage to the protective myelin sheath from damage to the axon itself and determine whether the inflammation is limited to one nerve or widespread.
Imaging and Necessary Investigations
Imaging techniques such as magnetic resonance imaging (MRI) and computed tomography (CT) are used to examine the vertebrae and spine and rule out nerve compression caused by a disc herniation or narrowing of the bony passages. In some complex cases, the doctor may perform a nerve or skin biopsy to assess damage to small nerve fibers under a microscope.
Surgery for Conditions Caused by Nerve Compression
When diagnostic tests and imaging show that the nerve inflammation is caused by clear mechanical compression—such as a disc herniation or entrapment of a nerve in the hand—and is accompanied by motor weakness or failure to respond to conservative treatment, surgery or microsurgical endoscopic techniques may become necessary to relieve pressure and save the nerve from permanent damage.
Tips for Relieving the Symptoms of Peripheral Neuropathies
Daily care and a healthy lifestyle help improve quality of life and reduce the bothersome complaints associated with nerve damage. Following preventive recommendations protects the limbs from complications and supports recovery alongside medical treatment for peripheral neuropathies.
Important home-care tips and measures include:
-
Take excellent care of the feet and hands: Inspect the feet daily for wounds, blisters, or unnoticed ulcers. Wash them with warm water, dry them thoroughly, and moisturize the skin to prevent cracking.
-
Choose suitable shoes and socks: Wear comfortable, wide medical shoes that do not compress the toes. Use soft cotton socks without prominent seams to avoid direct friction with sensitive skin.
-
Exercise regularly: Perform light exercise such as walking or swimming for 30 minutes a day. This improves circulation to the limbs, helps control blood sugar, and strengthens the muscles.
-
Avoid harmful habits: Stop smoking completely because it narrows the blood vessels supplying the nerves and worsens nerve damage. Also avoid alcohol, which has a direct toxic effect on nerve fibers.
-
Avoid positions that cause continuous pressure: Do not cross one leg over the other for long periods or lean excessively on the elbows, in order to avoid mechanical pressure on the main peripheral nerves.
Can Peripheral Neuropathies Be Cured Permanently?
Complete recovery and the possibility of permanently treating peripheral neuropathies depend on the underlying cause and how early the condition is detected. Early intervention provides very high chances of nerve-fiber regeneration and complete reduction of symptoms.
The possibility of complete recovery depends on the following situations:
-
Conditions that can be completely cured: If the neuropathy is caused by vitamin B12 deficiency, medication side effects, or temporary nerve compression, the nerve may return to normal once the deficiency is corrected, the medication is stopped, or the pressure is removed.
-
Chronic conditions—control and prevention of progression: In conditions such as diabetic neuropathy and autoimmune diseases, damaged nerve tissue may not be fully repaired if the damage is advanced. However, comprehensive treatment can completely stop deterioration, relieve pain and numbness, and restore the patient’s ability to move normally without discomfort.
How Long Does Treatment for Peripheral Neuropathies Take?
The time required for treatment and noticeable improvement varies from one patient to another. Nerve fibers grow and regenerate slowly, at a rate of approximately 1–2 millimeters per day, so recovery requires patience and adherence to the medical protocol.
Recovery time depends on the cause and extent of nerve damage:
-
Conditions caused by modifiable factors: After correcting vitamin B12 deficiency or treating mild mechanical compression, improvement begins within 4–8 weeks, while complete recovery may take several months.
-
Chronic conditions, such as diabetes: It usually takes 3–6 months of blood-sugar control and adherence to nerve-supporting medications to control pain and achieve comfort and stability.
-
Conditions caused by sciatica or disc compression: Conservative treatment and physical therapy generally require 6–12 weeks to reduce inflammation and restore normal movement.
When Are Peripheral Neuropathies Dangerous?
Peripheral neuropathies become serious and require intensive, urgent medical intervention when the nerve fibers begin to sustain severe damage or when inflammation extends to the motor nerves and autonomic nerves that control the internal organs.
The condition is serious and requires caution in the following situations:
-
Involvement of the autonomic nerves (autonomic neuropathy): Disturbances in blood-pressure regulation, such as a severe drop upon standing, a reduced heart rate, or serious digestive and bladder problems.
-
Advanced motor weakness: Damage extending to the motor nerves, causing rapid muscle atrophy, loss of the ability to walk, or difficulty gripping objects.
-
Complete loss of sensation and ulcer formation: Complete loss of pain and temperature sensation in the feet, leading to unnoticed wounds and complicated ulcers, such as diabetic foot ulcers, which may progress to bone infection or gangrene.
-
Rapid spread and severe pain: Motor weakness or numbness spreading upward from the feet to the legs and hands over a short period, which may indicate an acute autoimmune disease requiring immediate evaluation.
Signs That Require Immediate Medical Consultation
Although neuropathy symptoms may develop slowly, certain warning signs indicate rapidly progressing nerve damage or severe compression requiring urgent medical intervention to prevent permanent complications in the nerve and muscle tissue.
The most important symptoms requiring immediate medical evaluation include:
-
Sudden or progressive motor weakness: Sudden difficulty lifting the foot, persistent stumbling, or inability to grip objects, causing them to fall from the hands.
-
Rapid spread of numbness: Numbness and muscle weakness quickly extending from the fingertips toward the legs or arms over several days or weeks.
-
Complete loss of temperature or pain sensation: Total absence of sensation to external stimuli, exposing the limbs to burns or wounds without the patient noticing.
-
Wounds or ulcers that do not heal: Ulcers or changes in the color of the skin on the feet, especially in patients with diabetes, without pain; this may warn of diabetic foot complications.
-
Internal-organ disturbances: Severe dizziness when standing, sudden changes in heart rate, or problems controlling the bladder or bowel.
#call#
Treatment of Peripheral Neuropathies with Professor Dr. Ramadan Shams El-Din
Accurate diagnosis and a customized treatment plan are the foundation for controlling neuropathy and protecting tissues from damage. Treating peripheral neuropathies requires advanced medical expertise to distinguish between the underlying causes and provide the best available options for each patient.
Professor Dr. Ramadan Shams El-Din offers a comprehensive medical approach based on the latest international standards and protocols for managing various cases of peripheral neuropathy, whether caused by metabolic diseases such as diabetes or by nerve-root and disc compression in the spine.
Medical services and care under Professor Dr. Ramadan Shams El-Din include:
-
Advanced and accurate diagnosis: Using the latest nerve-conduction and electromyography technology, together with detailed MRI analysis, to precisely assess nerve-fiber function.
-
Medication and interventional management: Developing customized medication protocols to relieve severe pain, along with advanced image-guided local injection techniques to reduce inflammation of the nerve roots.
-
Rehabilitation and balance-restoration programs: Designing targeted physical-therapy and motor-rehabilitation plans to strengthen the muscles surrounding the affected nerves, restore balance, and prevent falls.
-
Precise surgical solutions when necessary: Using microsurgical and endoscopic techniques to remove mechanical pressure from the nerves in cases of nerve entrapment or disc herniation, achieving high success rates and a rapid recovery period.
#call#